Operative Dictations in Urologic Surgery
Armenakas NA, Fracchia JA, Golan R. Vasectomy. Chapter 46. Wiley, 2019
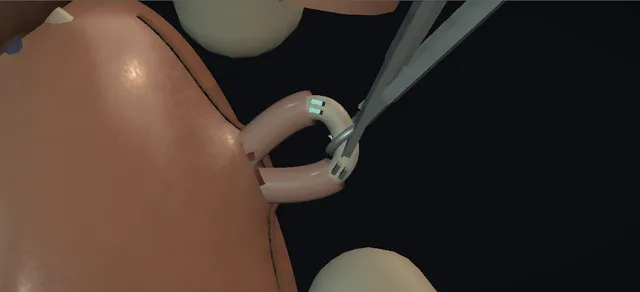
Followed for the indication, the four essential steps and the template dictation. Consent includes the contraceptive alternatives; supine, preparation and a time-out; both vasa palpated and local anaesthetic given into the scrotum. Access is by one incision on the upper median raphe or two anterolateral ones. The vas is grasped with a ring-tipped fixation clamp and brought into the wound, its fascia incised and a segment of about a centimetre isolated. A clip goes on each end, the segment is divided out and sent to pathology, and both ends and lumens are cauterised, with haemostasis throughout. The same is done on the other side, the skin closed with an absorbable suture, and a dressing and a support applied. Two variations are used: the scrotal wall pierced with a sharp-tipped curved haemostat (the no-scalpel technique) for access, and the sheath closed over the remnant for occlusion. The complication list (bleeding, infection, swelling, a vessel ligated in mistake for the vas, pain, recanalisation) supplies the three states. General practice, not from the chapter: the three-finger hold, the right side first, the sheath over the abdominal rather than the testicular end, a puncture closed with one stitch, and every first, escalate and document step.
Open guideline
BAUS
British Association of Urological Surgeons. Vasectomy: information about your procedure. Leaflet A24/049, published October 2024, read 18 October 2026
Regard as irreversible; not sterile until the all-clear from post-operative semen tests after at least 12 weeks and 20 ejaculations, with 20 to 30 ejaculations needed on average; if a few sperm remain, a further sample a few weeks later. Late failure 1 in 2000. Early failure, persistent motile sperm, 1 in 250. Troublesome chronic testicular pain affecting day-to-day activities in 1 to 2 in 100. Mild bruising and swelling in almost all; blood in the semen the first few times in between 1 in 2 and 1 in 10. No evidence of long-term health risks such as testicular or prostate cancer. A general anaesthetic is advised when the tubes are difficult to feel. Absorbable skin stitches.
Open guideline
European Urology
Dohle GR, Diemer T, Kopa Z, Krausz C, Giwercman A, Jungwirth A. European Association of Urology guidelines on vasectomy. Eur Urol 2012;61:159-163
Abstract read 18 October 2026. Counselling to include alternative methods of contraception, complication and failure rates and the need for postoperative semen analysis; informed consent before the operation. Mucosal cautery and fascial interposition reduce early failure compared with simple ligation and excision; no robust data show one technique superior in preventing late recanalisation and pregnancy. Clearance can be given for azoospermia or rare non-motile sperm at least 3 months after the procedure. The current EAU sexual and reproductive health guideline has no vasectomy chapter; this is the EAU document on the operation.
Open guideline
BMC Medicine
Sokal D, Irsula B, Hays M, Chen-Mok M, Barone MA. Vasectomy by ligation and excision, with or without fascial interposition: a randomized controlled trial. BMC Med 2004;2:6
Abstract read 18 October 2026. 841 men at eight clinics in seven countries, all by the no-scalpel approach, randomised to ligation and excision with or without fascial interposition. Fascial interposition shortened the time to azoospermia (hazard ratio 1.35) and reduced failures based on semen analysis from 12.7% to 5.9%. Slightly more adverse events with interposition, not significant.
Open guideline
Cochrane Database of Systematic Reviews
Cook LA, Pun A, Gallo MF, Lopez LM, Van Vliet HA. Scalpel versus no-scalpel incision for vasectomy. Cochrane Database Syst Rev 2014;(3):CD004112
Abstract read 18 October 2026. Two randomised trials. The larger found less perioperative bleeding, pain during surgery, scrotal pain and incisional infection with the no-scalpel approach; both found less haematoma (odds ratio 0.23). Faster operations and quicker return to sexual activity; no difference in effectiveness.
Open guideline