
140 operations · 104 drills · one place
What you see. Where you are.
The operative view, the anatomy around it, and the decision that follows. Prepare for your next case.
1 of 5 · Quick tour
Find your operation in 3D.
Browse the operative models below. Search by operation or anatomy, then open a scene.
Start free · No account needed
Six featured AR lessons
Bring the operation into your room.
Choose a lesson and explore the original operative anatomy. The gleaming button guides your next action.
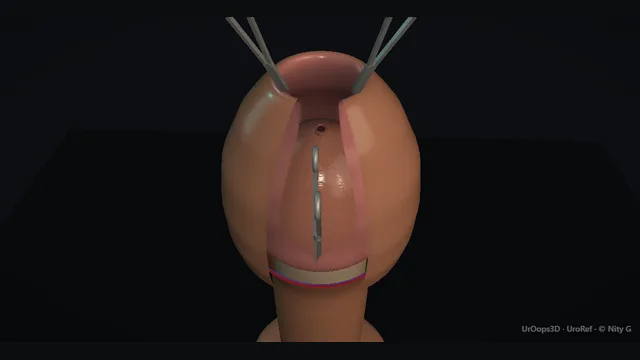
Phone AR · Desktop 3D
Adult circumcision
On your phone, choose Animated lesson in AR, start the camera, find a surface, then Place model. Follow the highlight through the lesson.
Open on a phone to use AR
Click me next: open adult circumcision.
On a desktop, choose View in 3D, or Audience QR in the lesson to open it on your phone.
Teaching only · schematic anatomy
The operative atlas
Find your next operation.
Showing 12 of 140 animations
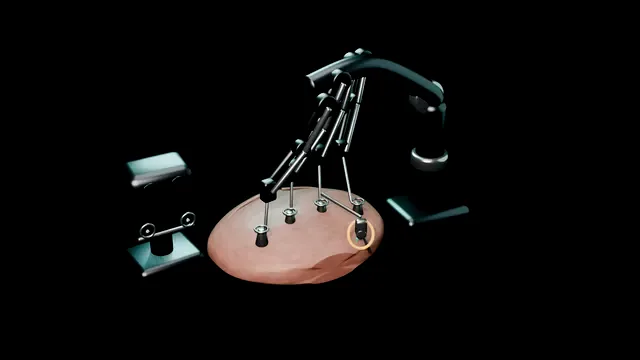
Robotic surgery: the basics
Console, cart and wristed arms: why the robot exists, how it docks, what it buys, and the haptics it never had. Emergency undock drilled.
Robotic
Ureteroscopy + laser
Safety wire first, a second wire through the semirigid scope, the ureter tented on both and the scope railroaded up the left ureter. Dusting, never large fragments; clearance by gravity, basket if needed; a selective stent. Perforation, avulsion and the impacted stone.
Stones
Flexible ureterorenoscopy
Access sheath, calyx mapping, lower-pole dusting. Pressure, backflow and the bleed that takes the view.
Stones
Percutaneous nephrolithotomy
CT planning, calyceal puncture, tract dilation, clearance. Pleura, colon and the bleed that needs embolisation.
Stones
Percutaneous nephrostomy
Decompression through a posterior calyx. Retrorenal colon, segmental arteries, the transpleural line.
Stones
TURP: the resection, beat by beat
Interactive through the resectoscope: landmarks, the median lobe, both lateral lobes released and dropped, the apex, Ellik, haemostasis, catheter.
Prostate
Laser enucleation
The enucleation plane, three lobes, the sphincter moment at the apex and morcellation in a full bladder.
Prostate
Bladder tumour resection
Map, exophytic tumour, base down to detrusor, the lateral-wall obturator moment and the orifice in the field.
Prostate
Radical nephrectomy
Artery first, vein second, upper pole and neighbours. The renal vein tear, the spleen, the pancreatic tail.
Renal + oncology
Partial nephrectomy
Clamp, pale kidney, tumour out with a rim, two-layer renorrhaphy, reperfusion. Leak and the delayed bleed.
Renal + oncology
Anderson-Hynes pyeloplasty
The crossing vessel at the PUJ, dismembering, transposition and the anastomosis over a stent.
Renal + oncology
Radical prostatectomy
Bladder neck, seminal vesicles, Denonvilliers’ plane, nerve-sparing pedicles and the apex.
Renal + oncology
Radical inguinal orchidectomy
Inguinal, never scrotal: delivery through the canal, high ligation at the internal ring.
Renal + oncology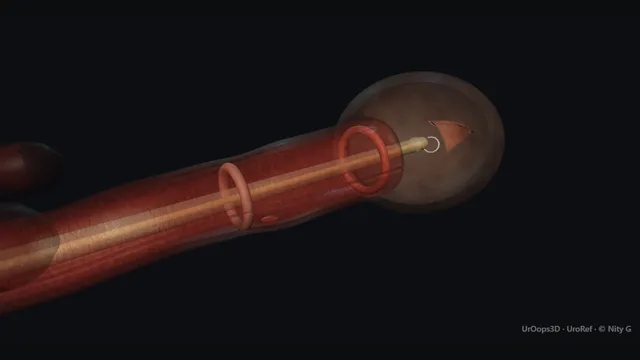
Optical urethrotomy
The stricture ring, the wire through the lumen, the cold knife and why the spongiosum decides the position.
Continence + urethra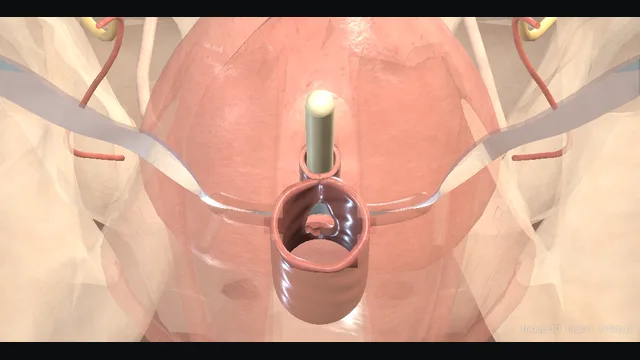
Transobturator sling
Mid-urethra, para-urethral tunnels, the trocar through the obturator foramen and the retropubic danger it avoids.
Continence + urethra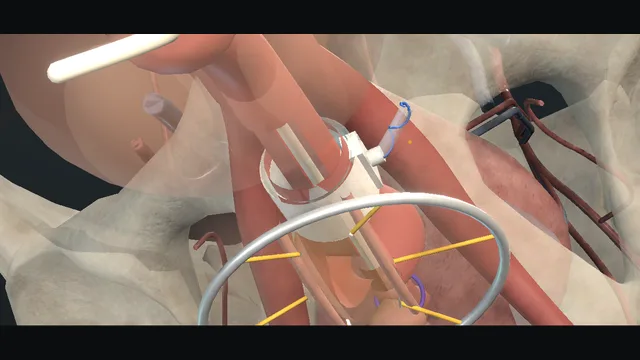
Artificial urinary sphincter
Bulbar cuff sizing, retropubic balloon, scrotal pump and cycling. Erosion, infection, the atrophy that leaks again.
Continence + urethra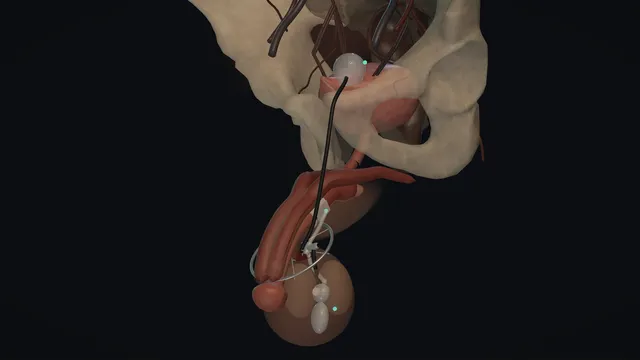
AUS: penoscrotal approach
One upper scrotal incision for all three parts: the cuff sized and locked, the balloon through the external ring, the pump in a dependent pouch.
Continence + urethra
Sacral neuromodulation
S3 foramen needle, motor responses, tined lead and the two-stage trial. Wrong level, infection, migration.
Continence + urethra Adult circumcision
Dorsal slit, frenular artery, sleeve excision and the suture line. Bleeding, urethral injury, meatal stenosis.
Genital
Scrotal exploration: torsion
The bell-clapper cord, derotation, the viability decision and bilateral fixation. Time is tissue.
Genital
Suprapubic catheter
A filled bladder, a clear window, a midline track. The bowel between wall and an empty bladder is the whole danger.
Emergency + trauma
Blunt renal trauma
One kidney, five grades and the decisions between them: embolise, explore or watch.
Emergency + trauma
Combined intrarenal surgery
Supine, one position, two scopes: retrograde and percutaneous at the same time. The colon moves when the patient does.
Stones
Cystolitholapaxy
Fibre or stone punch, evacuate, then ask why it formed. The punch closes only on a stone lifted to the centre of the bladder.
Stones
The forgotten stent
The stent that never came back, crusted from both ends. Decrustation, staged removal and the register that prevents it.
Stones
Intravesical botulinum toxin
A dome-to-wall injection map that spares the trigone. Retention is planned for, not discovered.
Continence + urethra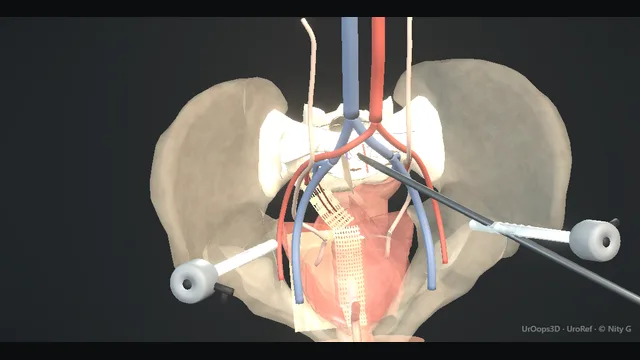
Laparoscopic sacrocolpopexy
The vault lifted to the promontory. Presacral veins, ureters, and the mesh that must be covered.
Continence + urethra
Bulbar urethroplasty
Short strictures excised and joined; long ones grafted from the cheek. Tension is the enemy.
Continence + urethra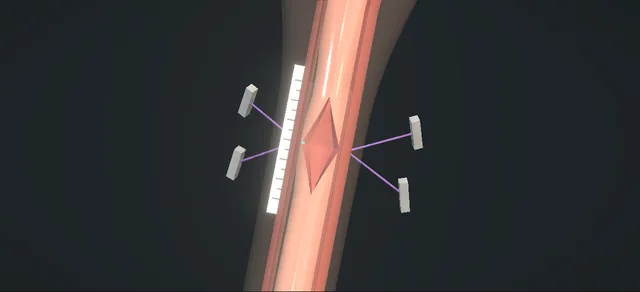
Augmented anastomotic urethroplasty
The scar excised, both ends opened dorsally, the ventral walls joined in two layers and an oral graft quilted to the corpora in the dorsal diamond.
Continence + urethra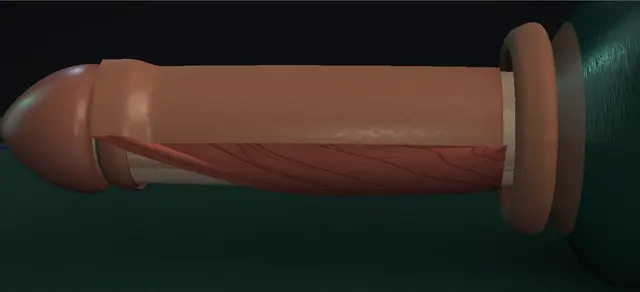
Penile skin flap urethroplasty
A ring of distal penile skin on its dartos pedicle: two cuts in two planes, the ring opened to a strip, brought round and turned over on to the opened urethra, skin to the lumen.
Continence + urethra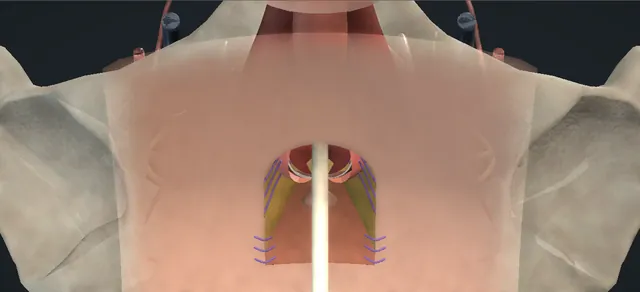
Perineal urethrostomy: inverted-U flap
An inverted-U flap turned into a ventral bulbar urethrotomy. A broad base, the apex stitch, mucosa to skin all round; stenosis is the late failure.
Continence + urethra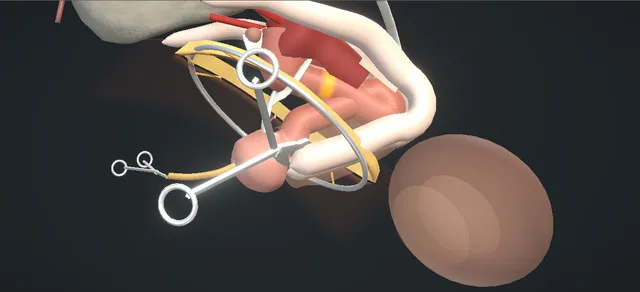
Male urethrectomy
The whole urethra out through the perineum after cystectomy: off the corpora to the glans, the meatus cored out, the bulbar arteries tied, the stump freed from under the bowel.
Continence + urethra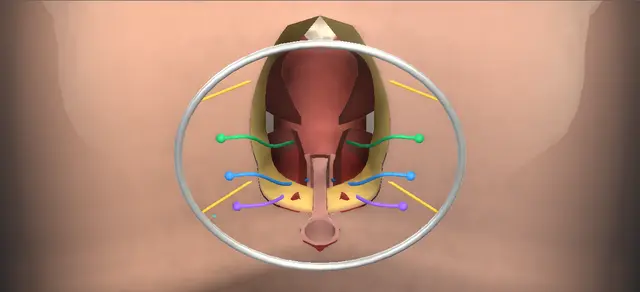
York-Mason fistula repair
A rectourethral fistula after prostatectomy, repaired from behind: each sphincter layer divided and marked with its pair, the track excised, three suture lines that do not overlie, every layer tied back to its partner.
Continence + urethra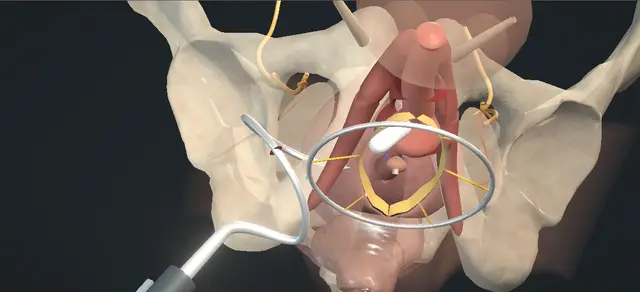
Male urethral sling
A transobturator sling after prostatectomy: the bulb bared, the central tendon cut, a helical passer round each ramus, the body fixed on the bulb and the bulb drawn up.
Continence + urethra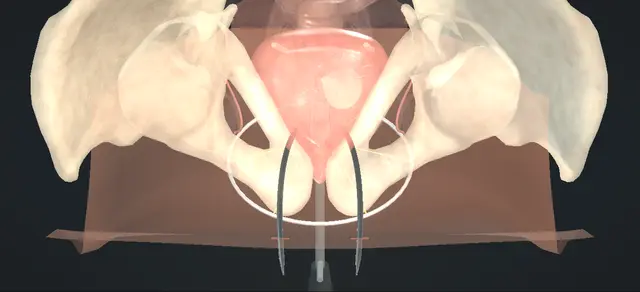
Retropubic sling
A tape under the mid-urethra, each arm carried up the back of the pubis on a trocar: the bladder drained and looked at before the tape is drawn, and the tape left loose.
Continence + urethra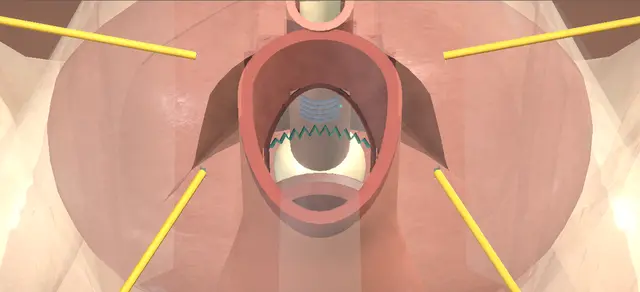
Female urethral diverticulectomy
An inverted-U flap, the periurethral fascia opened across and kept, the sac taken whole at its neck, and three closure lines that never lie on one another.
Continence + urethra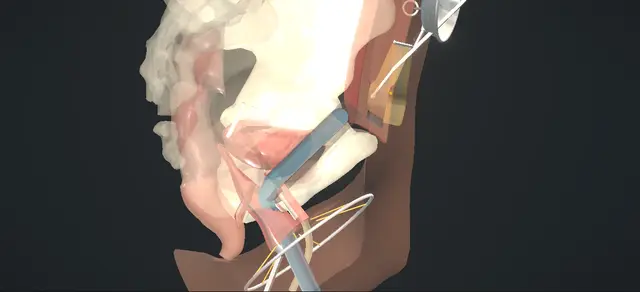
Autologous pubovaginal sling
A strip of rectus sheath under the bladder neck: the finger tunnel on the back of the pubis, the carrier on to the finger, cystoscopy before the tie, and a loose knot.
Continence + urethra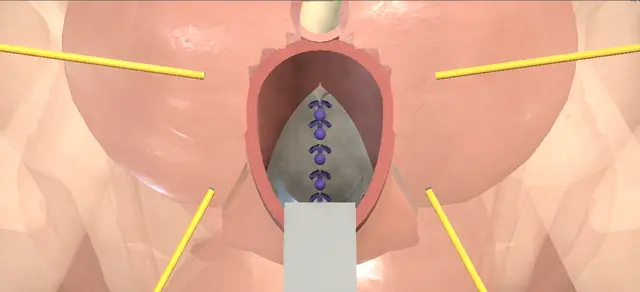
Anterior vaginal prolapse repair
Native-tissue cystocele repair: flaps off the pubocervical fascia, a midline plication that lifts the bladder, the fascia sutured back to the arcus on each side.
Continence + urethra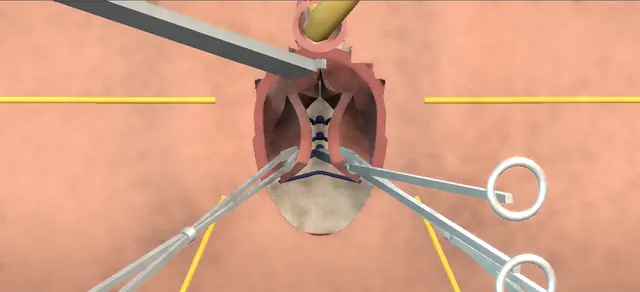
Rectocele repair
A triangle of posterior wall excised, the rectovaginal fascia plicated over the rectum with shallow bites, the perineal body rebuilt, and two fingers before closure.
Continence + urethra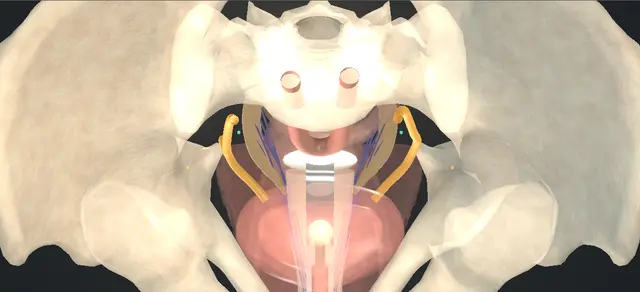
Uterosacral vault suspension
The vault brought out, the enterocele opened and the bowel packed away; three sutures through each uterosacral ligament lift the apex, then cystoscopy for ureteric efflux.
Continence + urethra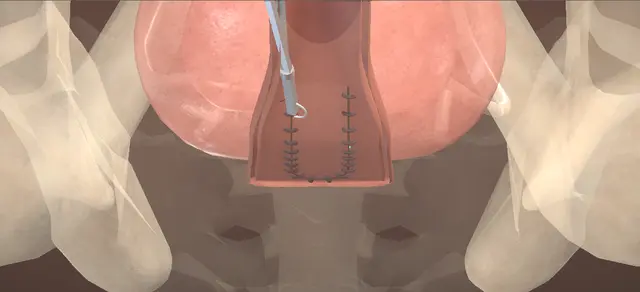
Vesicovaginal fistula repair, transvaginal
A fistula at the vault after hysterectomy, closed through the vagina: an inverted-U flap, the tract excised to the detrusor, two crossed bladder layers, a dye test and the flap advanced as a third.
Continence + urethra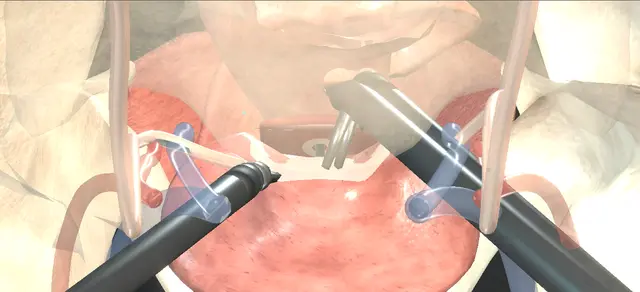
Robotic vesicovaginal fistula repair
A persistent vault fistula repaired from above: catheters up both ureters and through the tract, bladder parted from vagina, two closures crossed and omentum between them.
Continence + urethra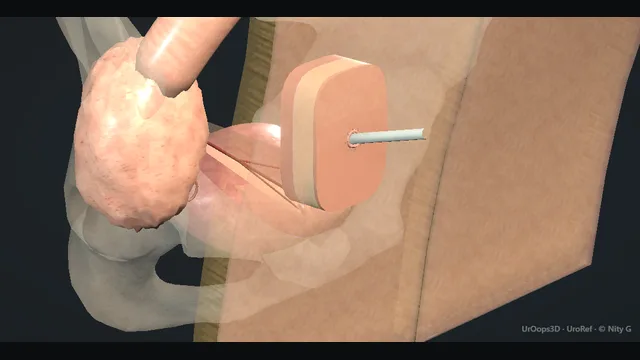
Mitrofanoff channel
The appendix becomes a catheterisable channel with a flap-valve tunnel. Stenosis is the long-term enemy.
Continence + urethra
Penile fracture repair
The buckling moment, the tear in the ventrolateral tunica, the degloving that finds it.
Genital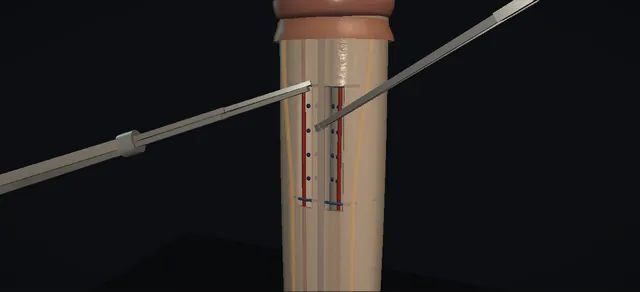
Penile plication: Lue sixteen-dot
Sixteen dots either side of the deep dorsal vein, four sutures through tunica only, folds that take the bend out. The second erection is the proof.
Genital
Ischaemic priapism: shunt
Aspirate, irrigate, sympathomimetic, then the distal shunt. The clock decides the outcome.
Genital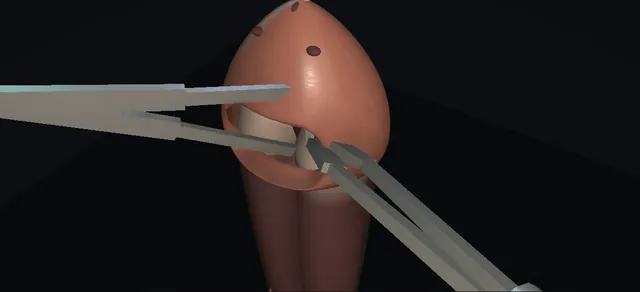
Al-Ghorab open distal shunt
The open shunt after the ladder has failed: a transverse glans incision, a window in each corporal tip, bright blood as the endpoint.
Genital
Varicocele: coil or ligature
Coils up the vein or ligation below the ring. The lymphatics decide the hydrocele.
Genital
Hydrocele repair
Drain, evert the tunica behind the testis and cord, close loosely enough for a little finger. The haematoma is the complication the dressing is for.
Genital
Inflatable penile prosthesis
Two cylinders, a pump, a reservoir. Dilation crossover and the paravesical corner.
Genital
Malleable penile prosthesis
One rod in each corpus and nothing else. The lateral wall, the two readings, the fold and the bend.
Genital
Penile arterial revascularisation
Inferior epigastric artery to the dorsal artery, end to side under the microscope. Selection is the operation; a twist in the tunnel is the failure.
Genital
Penile reimplantation
The part out of iced water, the two cut faces lined up on a catheter, then joined from the inside out: corpora, urethra, vein, artery, nerve, skin.
Genital
Radical cystectomy + conduit
The bladder out, the bowel in, the stoma marked. Rectum behind, ureters above, plexus below.
Renal + oncology
Radical cystectomy + PLND: pelvic atlas
A Blender-built male pelvis: ureters over the bifurcation, pedicles off the anterior division, the obturator fossa cleared.
Renal + oncology
Open supratrigonal cystectomy + ileal conduit
Benign disease, open: layers of the wall, the trigone kept, fifteen centimetres of ileum, Bricker joins over stents, a spouted stoma.
Continence + urethra
Nephroureterectomy + cuff
Kidney and whole ureter with a true bladder cuff. No-touch, because spillage seeds.
Renal + oncology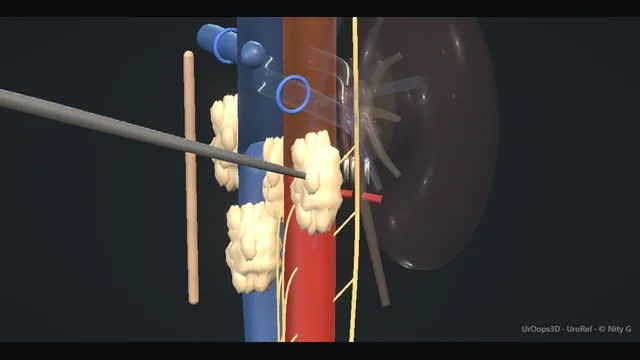
Retroperitoneal node dissection
The post-chemo mass on the great vessels. Lumbar veins, sympathetic chains, chyle.
Renal + oncology
Partial penectomy
A clear margin with the function that remains. Spatulated urethra, reconstructed tip.
Renal + oncology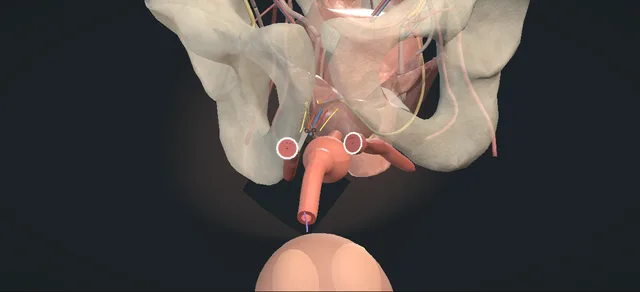
Total penectomy with perineal urethrostomy
The whole penis for a cancer too proximal for a stump. Urethra divided long, each crus divided and closed, the end drawn beneath the scrotum to a wide perineal opening.
Renal + oncology
Hypospadias repair
The plate incised, tubularised, covered. The fistula is the complication every parent asks about.
Paediatric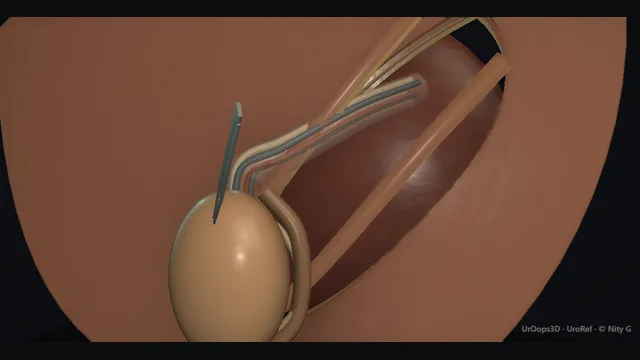
Orchidopexy
Down the canal without tension into a sub-dartos pouch. The vessels set the limit.
Paediatric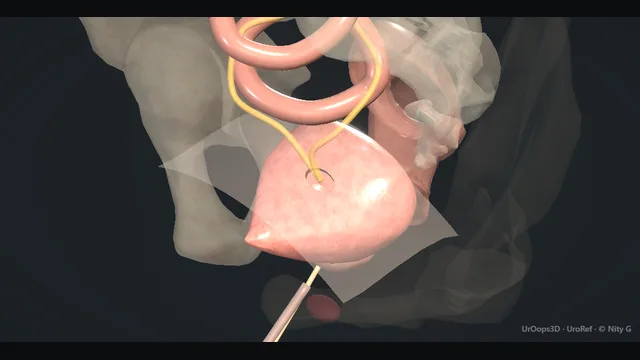
Bladder rupture
A properly filled cystogram, then the intraperitoneal from the extraperitoneal decision.
Emergency + trauma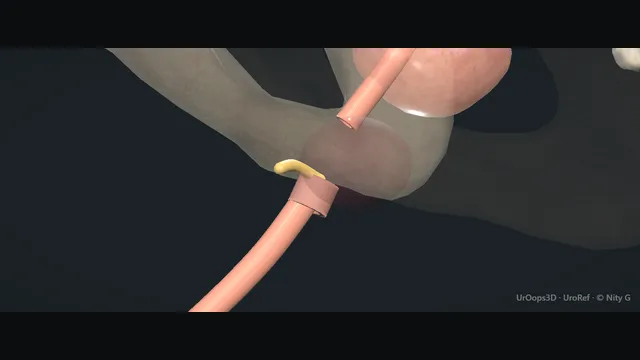
Pelvic fracture urethral injury
Blood at the meatus, a gentle study, a suprapubic drain and a plan made for months later.
Emergency + trauma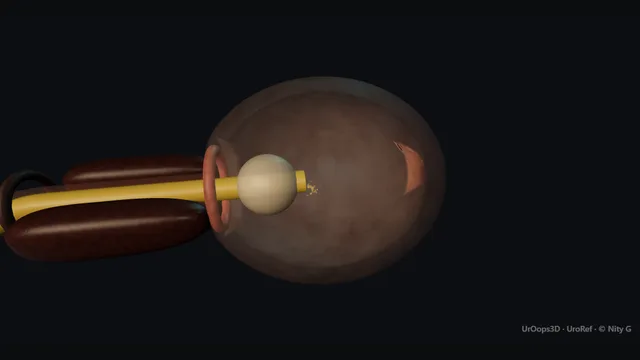
Urethral catheterisation, and the difficult one
Two curves and a sphincter, done blind: gel and time, the penis angle, breathing at the sphincter, urine before balloon. The ladder when it will not pass.
Emergency + trauma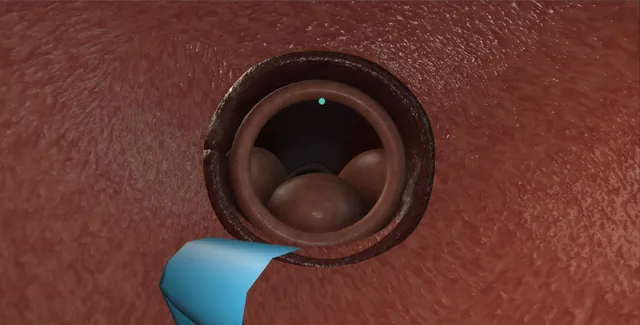
Flexible cystoscopy: the outpatient look
The urethra under vision, the bubble as the compass, the survey in a fixed order, retroflexion, a tumour mapped and a stent out through the channel.
Emergency + trauma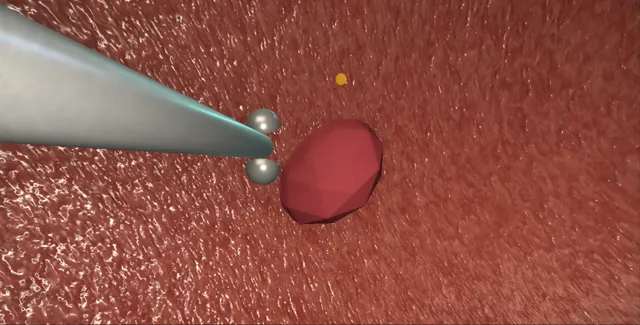
Rigid cystoscopy, biopsy and fulguration
Sheath in on the obturator, two lenses, a cold-cup bite taken unburnt, the button on the point, and mapping biopsies each in their own pot.
Emergency + trauma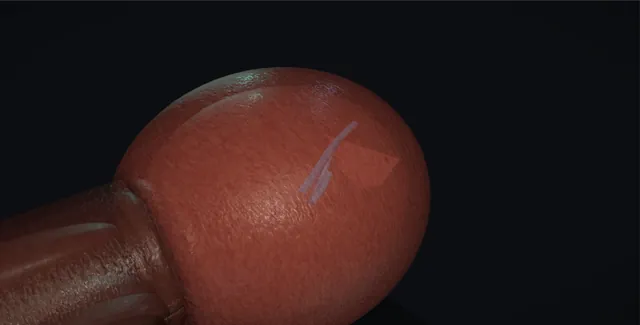
Retrograde pyelogram and JJ stent
The orifice centred, contrast gently, the wire that must curl, the stent over it with the pusher holding, both curls seen, the register.
Stones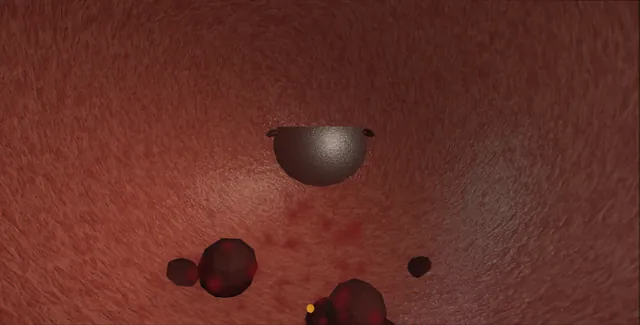
Clot retention: evacuation and haemostasis
The patient first, the bedside washout, the Ellik through a 26 French sheath, the survey before the prostate is blamed, arteries at their point, ooze to the catheter.
Emergency + trauma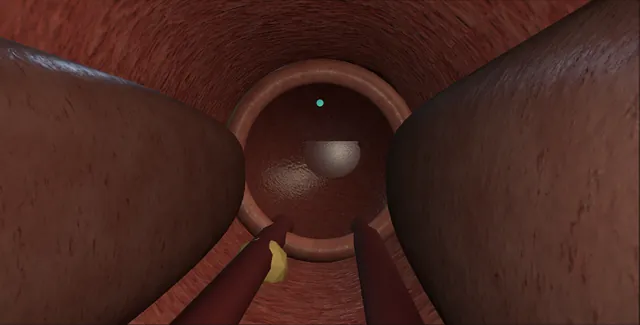
Bladder neck incision (TUIP)
The small gland and the tight neck: one Collings knife incision at seven, from just distal to the orifice through the neck towards the veru.
Prostate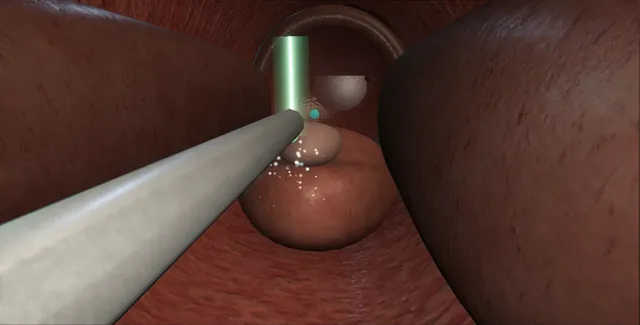
GreenLight laser vaporisation
Goggles on, the fibre a millimetre off the tissue, bubbles as the feedback; median lobe, laterals, apex last from the veru. The man on anticoagulants.
Prostate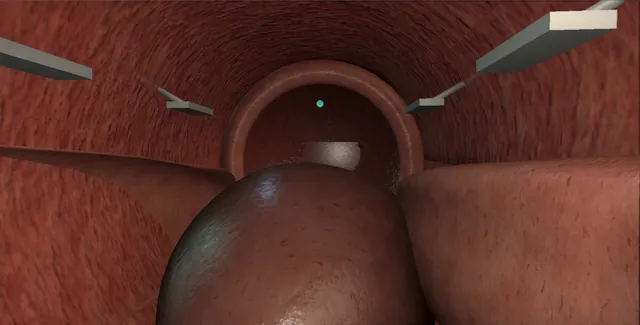
Prostatic urethral lift (UroLift)
Nothing cut: implants at ten and two from 1.5 cm inside the neck to a centimetre short of the veru, the lobes held apart, ejaculation kept.
Prostate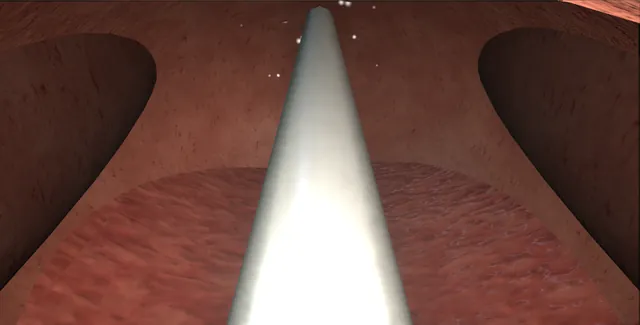
Rezum water-vapour therapy
A needle a centimetre into the transition zone and nine seconds of steam, a centimetre apart from the neck to the veru; a catheter expected, the result in weeks.
Prostate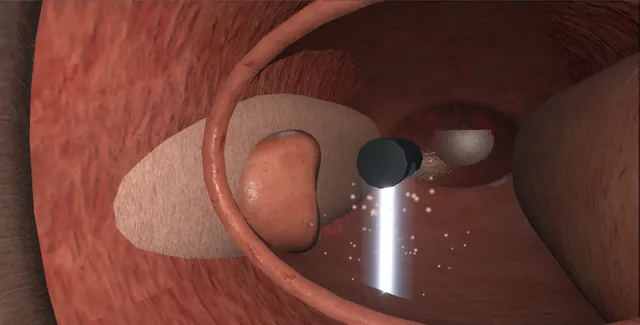
Aquablation: the planned waterjet
The contour drawn on the ultrasound from the veru and the orifices, the jet in four minutes, then the bleeding that is the surgeon's: cautery at five and seven, traction overnight.
Prostate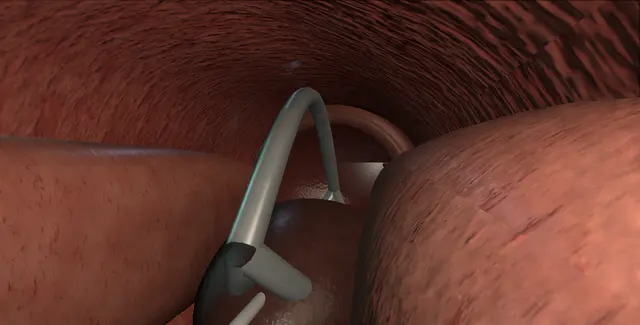
Temporarily implanted nitinol device (iTind)
Three struts at twelve, five and seven, the leaflet at six under the neck, five to seven days of pressure, then out on its suture; incisions made without a knife.
Prostate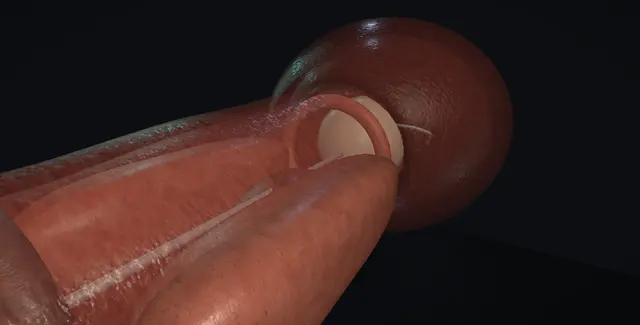
Optilume BPH: the drug-coated balloon
The distal lobe anchors in the bladder, the neck locks on the bladder neck, the working lobe splits the commissure at twelve, then paclitaxel for five minutes so it does not fuse back.
Prostate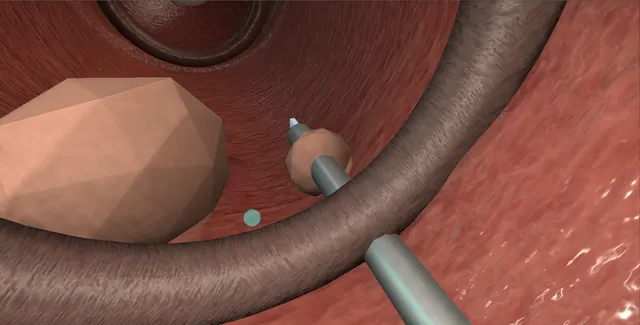
Posterior urethral valve ablation
The infant scope below the veru, the leaflets at five and seven, a cold knife or a bugbee on the lowest setting, and the sphincter a millimetre behind.
Paediatric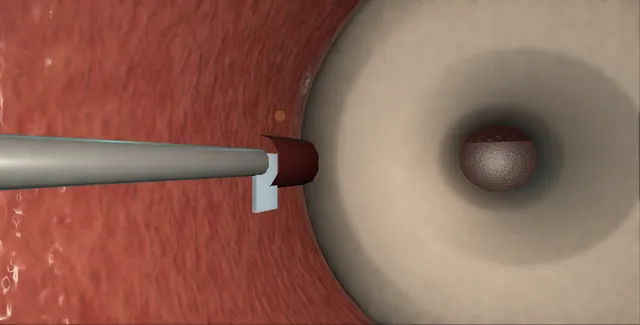
Bladder neck and anastomotic stenosis
A wire through the pinhole first, then a cold knife at three and nine, deep enough to see the fat and no deeper; steroid or mitomycin into the cuts, and the sphincter untouched.
Continence + urethra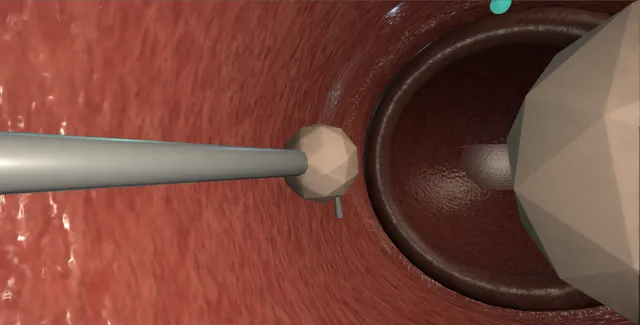
Urethral bulking injection
The needle a centimetre below the neck, submucosal at three and nine until the lumen closes to a slit; nothing cut, nothing burnt, and the second sitting expected.
Continence + urethra
Intravesical BCG
Two weeks after the resection, a dry bladder, an atraumatic catheter, the dose held for two hours; the six then the maintenance, and the fever that is not cystitis.
Renal + oncology
Immediate intravesical chemotherapy
Mitomycin within six hours of the resection, held for an hour, the bladder surveyed for a perforation before a drop goes in, and the drainage that follows.
Renal + oncology
Urodynamics
Two lines and a rectal catheter, the fill at a physiological rate, the cough that proves the trace, detrusor pressure as the number that matters, and the leak on the screen.
Continence + urethra
Augmentation cystoplasty
The bladder bivalved like a clam, twenty centimetres of ileum opened along its border and folded into a cup, sewn to the rim watertight; catheterisation for life.
Continence + urethra
Orthotopic neobladder
Fifty-five centimetres of ileum, forty detubularised and folded into a sphere, the afferent limb for the ureters, and the dependent point sewn to the urethral stump over a catheter.
Renal + oncology
Continent cutaneous diversion
The right colon opened along its taenia and closed as a reservoir, the ileum tapered over a 12 French catheter, the valve plicated, and a flush stoma to catheterise for life.
Renal + oncology
Bladder neck closure
The outlet that cannot be saved: the neck dissected off the prostate, the urethra divided, both ends closed in layers with omentum between, and a suprapubic for life.
Continence + urethra
Transperineal prostate biopsy
The MRI first, the probe in the rectum, the block at the apex, targeted cores through the lesion, systematic cores by sector, and the apex and anterior gland the transrectal needle never reached.
Prostate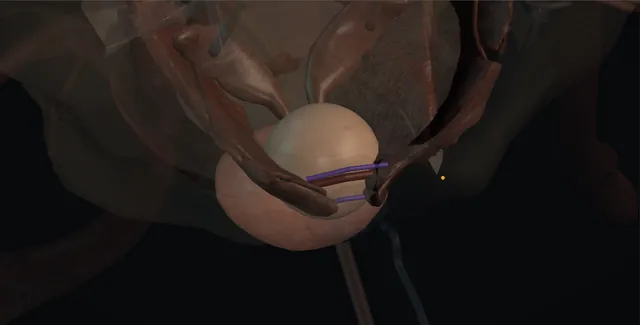
Simple prostatectomy
The hundred-gram gland: dorsal venous complex stitched, a transverse capsulotomy, the adenoma swept off the capsule and pinched off at the apex, five and seven o'clock, the capsule closed over a catheter.
Prostate
Prostatic artery embolisation
The CT angiogram is the operation: over the bifurcation, into the anterior division, the prostatic artery found where it was drawn, cone-beam CT for the non-target branch, microspheres to stasis, both sides.
Prostate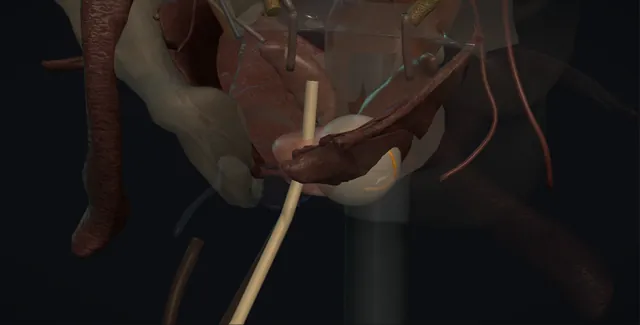
Focal ablation of prostate cancer
The lesion and its margin, short of the rectal wall, the urethra and the sphincter: HIFU from the rectum or cryotherapy from the perineum, watched at the edges, the other side and the bundle spared.
Prostate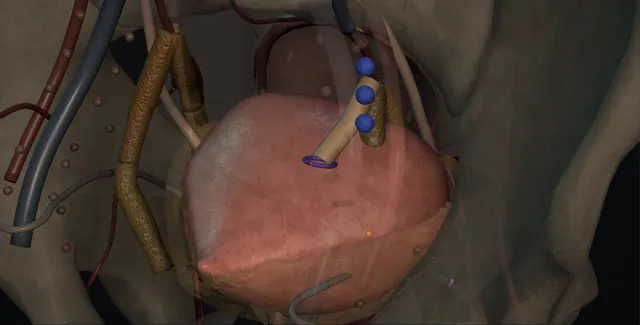
Distal ureteric reconstruction
The ureter at the brim with its adventitia, the bladder drawn up and hitched to the psoas past the genitofemoral nerve, a spatulated reimplant over a stent, and the Boari flap for the longer gap.
Renal + oncology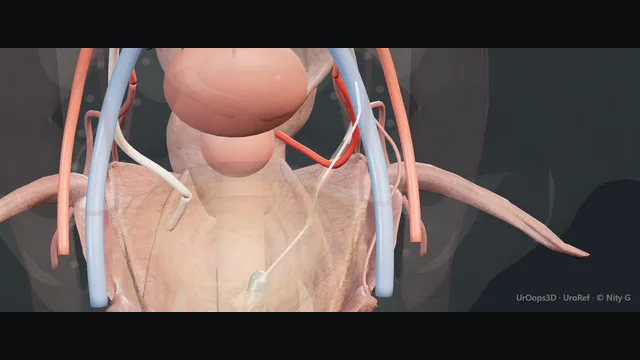
Ureteric injury: recognition and repair
Where the uterine artery crosses and at the brim: blue dye and the retrograde on the table, the clip off, the burn excised, the late urinoma drained, a nephrostomy, and repair by level when the patient is ready.
Renal + oncology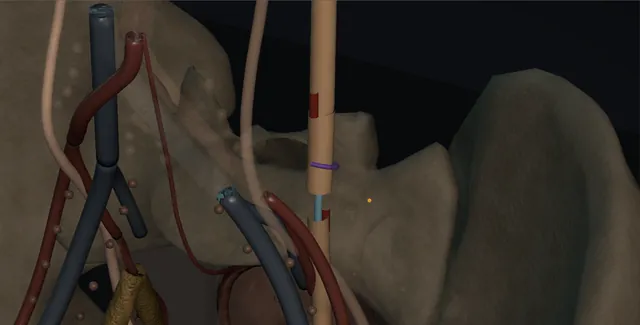
Ureteroureterostomy
The short mid-ureteric stricture: mobilised enough to meet and no more, excised to bleeding ends, spatulated on opposite sides, joined over a stent without tension, and wrapped in fat.
Renal + oncology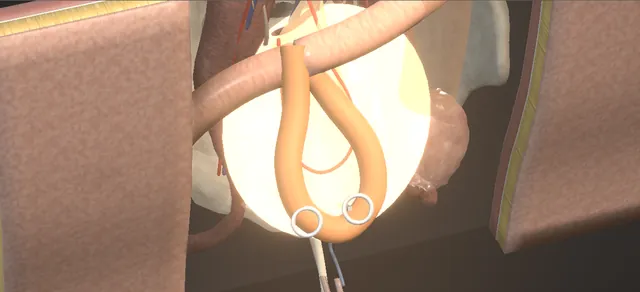
Ileal ureter
A long ureteric loss replaced with ileum on its pedicle: chosen against the light, laid isoperistaltic, joined to the pelvis and the bladder. The pedicle is the operation.
Renal + oncology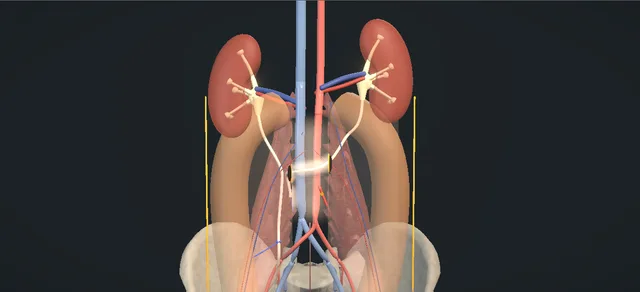
Transureteroureterostomy
One ureter joined to the other: the donor divided above the disease, drawn through a tunnel in front of the great vessels above the inferior mesenteric artery, and sewn end to side to the recipient.
Renal + oncology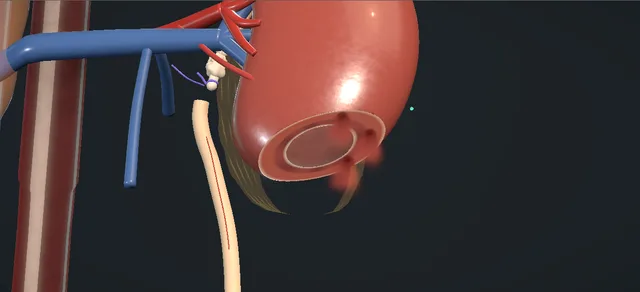
Ureterocalicostomy
No pelvis left to rebuild: the lower pole amputated to lay the dilated calyx open, the healthy ureter spatulated and sewn to it mucosa to mucosa over a stent.
Renal + oncology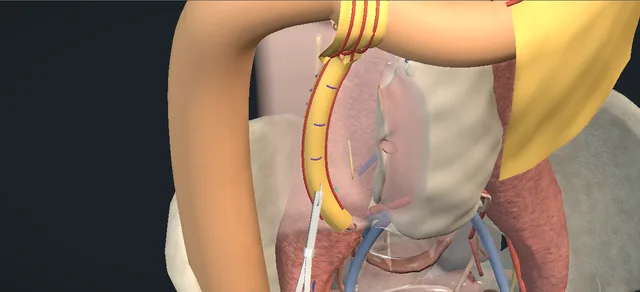
Ureterolysis with omental wrapping
The ureter trapped in retroperitoneal fibrosis: found above the plaque, biopsied, freed from above downwards with its adventitia on it, laid in the peritoneal cavity and wrapped in omentum.
Renal + oncology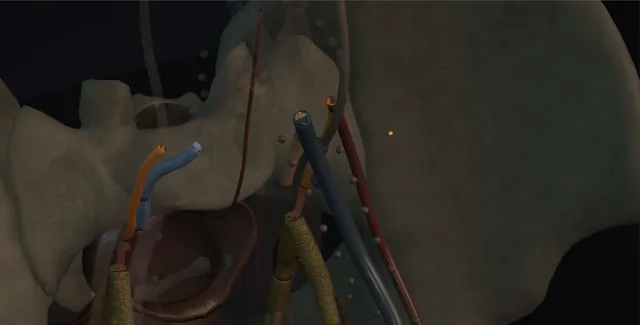
Pelvic exenteration
Bladder, prostate and rectum out as one piece: the internal iliacs ligated beyond the superior gluteal, the perineal phase, a conduit and a colostomy, and a flap so the pelvis is never empty.
Renal + oncology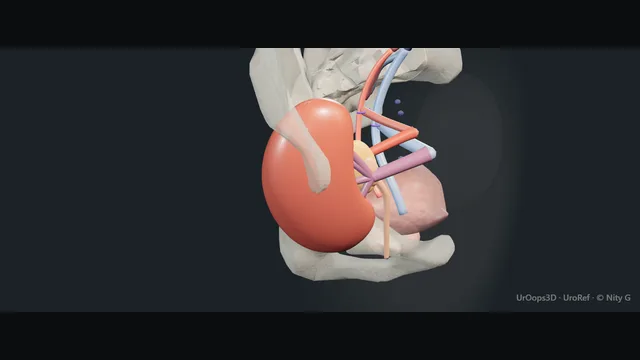
Recipient kidney transplantation
The kidney off the bench into the right iliac fossa: lymphatics tied, the vein end to side, the artery on its patch, reperfusion that pinks and passes urine, and the ureter into the bladder over a stent.
Renal + oncology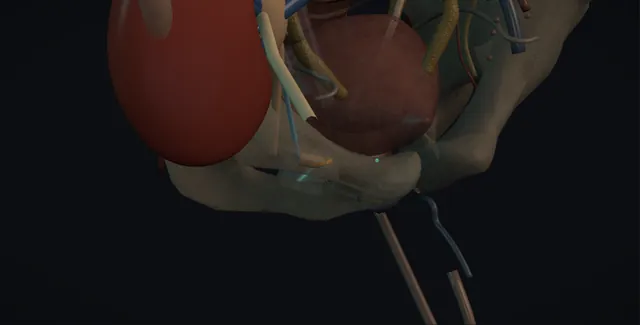
Transplant ureteric reconstruction
The ureter with the worst blood supply: the leak early, the stricture late, a nephrostomy and an antegrade stent first, then a redo reimplant, the native ureter to the graft, or a Boari flap.
Renal + oncology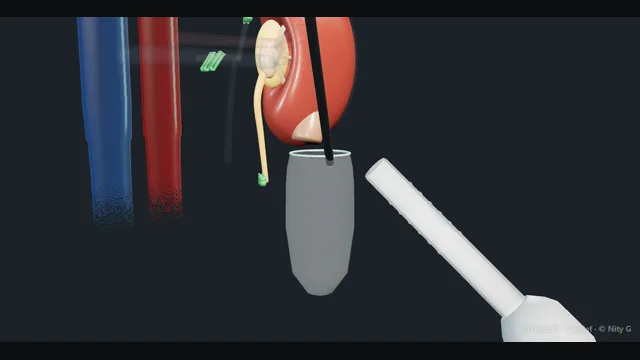
Living-donor nephrectomy
The left kidney off Gerota with the colon reflected, the gonadal vein as the road, the golden triangle kept, the adrenal and lumbar veins clipped, the artery clipped at the aorta, the vein stapled, and clip to ice.
Renal + oncology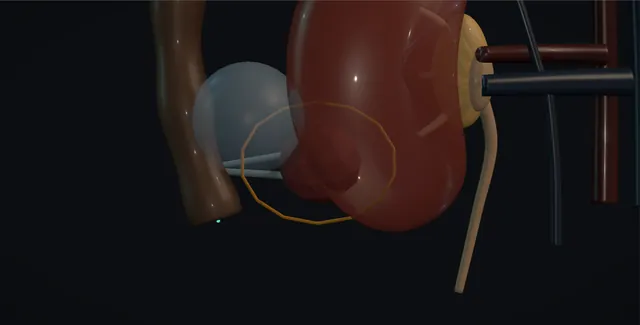
Renal tumour ablation
The small posterior mass in the wrong patient for surgery: biopsy first, the colon floated away, probes through the mass to its far edge, the ice ball watched past the margin, and the track ablated on the way out.
Renal + oncology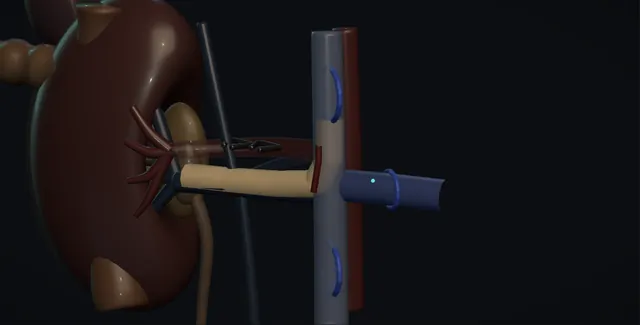
Renal vein and caval tumour thrombectomy
The tongue of tumour up the vein: the level sets the team, the artery first, three loops on the cava and the other vein, clamps in order, the cavotomy, the thrombus out whole, the cava closed wide.
Renal + oncology
Adrenalectomy
The endocrinologist first, the spleen and pancreatic tail rotated off the gland, the adrenal vein clipped before the gland is disturbed, the gland lifted by its fat and never grasped, and the short right vein into the cava.
Renal + oncology
Renal autotransplantation
A donor nephrectomy and a transplant on the same patient: the vessels taken long, the repair done cold on the bench, vein then artery in the iliac fossa, and the pelvis to the bladder when there is no ureter.
Renal + oncology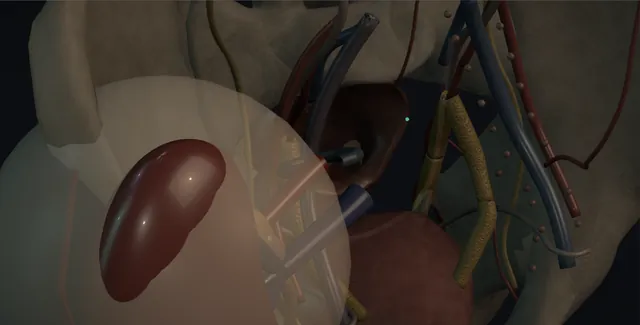
Transplant nephrectomy
The failed graft through the old scar: the subcapsular plane, the graft shelled out with the finger, the hilum clamped as one and oversewn in two layers, the ureter tied near the bladder, the capsule left behind.
Renal + oncology
Deceased-donor kidney retrieval
Brain death or circulatory death and their two clocks: the aorta and cava slung and cannulated, cross-clamp and cold perfusion, ice, the kidneys en bloc with Gerota on and the ureters long, separated on the bench, packed and documented.
Renal + oncology
Renal allograft biopsy
A creatinine up a fifth and only the tissue tells them apart: the superficial graft under ultrasound, cortex at a pole and away from the hilum, a two centimetre throw along the cortex, two cores, bed rest and the haemoglobin.
Renal + oncology
Paediatric pyeloplasty
The pelvis too big because the junction will not empty: the crossing vessel found and kept, the junction excised, the pelvis reduced, the ureter spatulated and joined dependently over a stent with 6-0 or 7-0.
Paediatric
Cohen ureteric reimplantation
Reflux that will not settle: the ureter freed on its cuff, drawn across the trigone under the mucosa, and sewn in on the far side. No twist, no kink, no tension.
Paediatric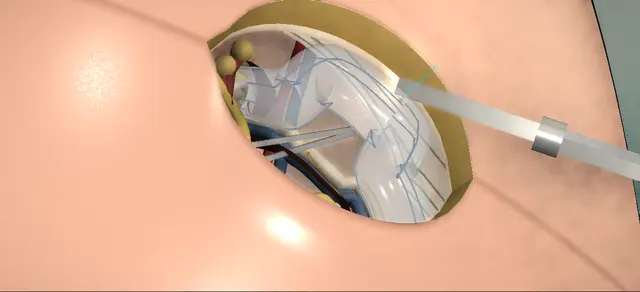
Paediatric inguinal hernia repair
Herniotomy in an infant: the canal opened along its fibres, the nerve kept, the sac freed from the vas and the vessels and tied at the deep ring.
Paediatric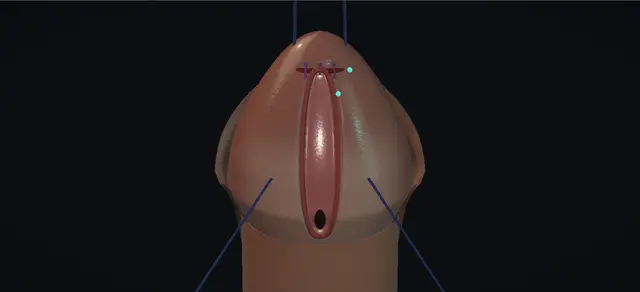
MAGPI hypospadias repair
A meatus at the corona on a straight penis. The bridge beyond it cut vertically and closed across, the ventral edge lifted on a hook, the glans closed under it in three layers. Nothing is tubularised.
Paediatric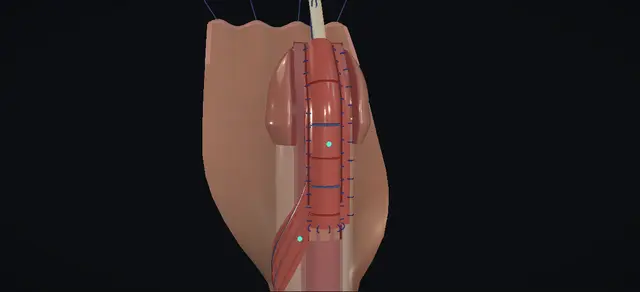
Hypospadias: onlay island flap
Mid-shaft hypospadias with the plate kept whole: an island of inner prepuce raised on its dartos, brought round the shaft and sewn on the plate over a stent.
Paediatric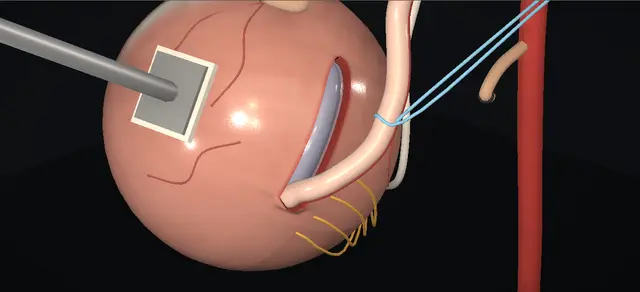
Extravesical ureteric reimplantation
Reflux repaired from outside the bladder: the obliterated artery divided, the detrusor split down to a bulging mucosa, the ureter laid in and the muscle closed loosely over it. The bladder is never opened.
Paediatric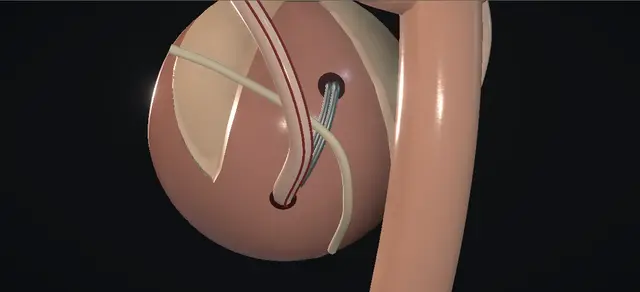
Politano-Leadbetter ureteric reimplantation
Reflux that will not settle: the ureter taken out of its own hiatus, round behind the bladder and in through a new one higher up, then tunnelled down to open where it always did.
Paediatric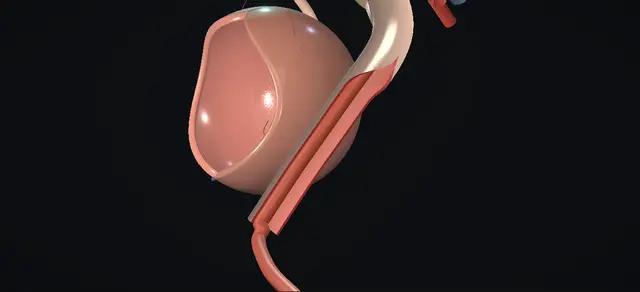
Megaureter repair
A ureter too wide to reimplant as it is: freed inside the bladder and then outside it, its narrow end removed, a strip of lateral wall excised over a catheter away from the medial vessels, and the tapered ureter drawn across the trigone under the mucosa.
Paediatric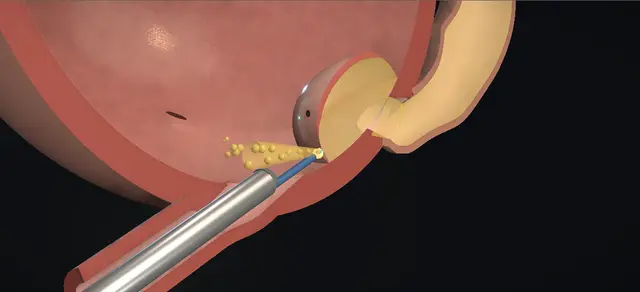
Ureterocele incision
An infected, obstructing ureterocele in a young child: one low transverse cut through the full wall, a jet of urine, and the bladder neck left alone.
Paediatric
Infected obstructed kidney: emergency decompression
Stone, fever and a falling pressure: sepsis six and the call to drain at the same time, prone for the posterior lower calyx or a stent from below, minimum contrast, the pus out tonight and the stone weeks later.
Emergency + trauma
Vasectomy: no-scalpel
Both vasa through one puncture: a loop delivered, a clip on each end, a segment to pathology, sheath over one end. Not sterile until the semen test says so.
Genital
Shock wave lithotripsy
The head coupled to the flank, the stone put in the crosshairs, the energy ramped and the stone broken; the rib, the skin-to-stone distance and the fragments.
Stones
Ureteroscopy for upper-tract tumour
Kidney-sparing treatment of a low-risk renal pelvic tumour: cytology before contrast, every calyx mapped, biopsy before the laser, the base whitened, a stent and a second look.
Renal + oncology
Inguinal lymph node dissection
Flaps raised with their fat, the groin packet lifted off the fascia lata from below, the saphenous vein kept, the deep nodes off the femoral vein, the sartorius over the vessels.
Renal + oncology
Posterior urethral reconstruction
After a pelvic fracture: the scar excised onto a sound from above, the crura parted for length, and the ends joined clockwise from twelve.
Continence + urethra
Acute paraphimosis
The retracted prepuce as a band behind the corona: block, compression and manual reduction, then punctures and a dorsal slit when it will not pass.
Genital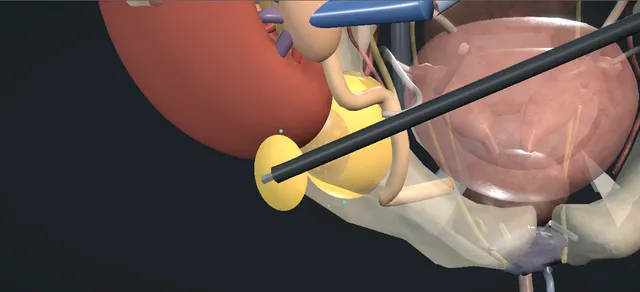
Transplant lymphocele
Lymph, not urine, on the fluid creatinine; a drain under ultrasound; then a wide laparoscopic window in the dome, with the transplant ureter found on the medial wall first.
Renal + oncology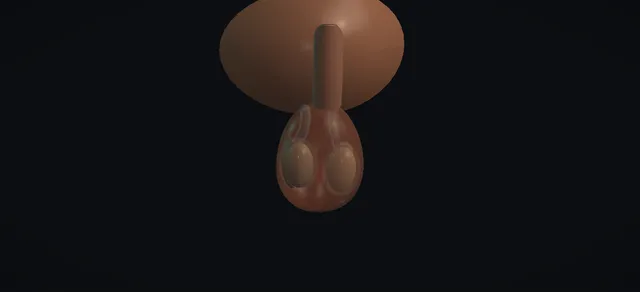
Vasectomy reversal
Scar cut out, the fluid on the slide decides, then mucosa and muscularis joined under the microscope. No sperm: the vas goes to an epididymal tubule.
Genital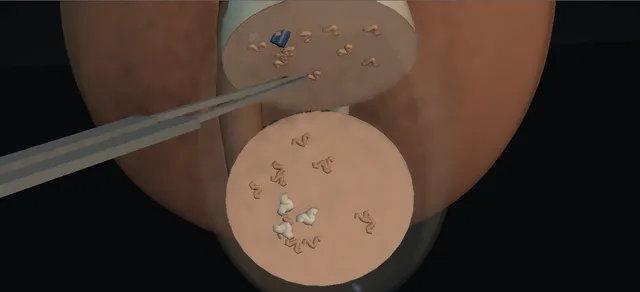
MicroTESE
The testis opened like a book between its vessels, dilated tubules picked out under the microscope, the laboratory result, and the other side when none is found.
Genital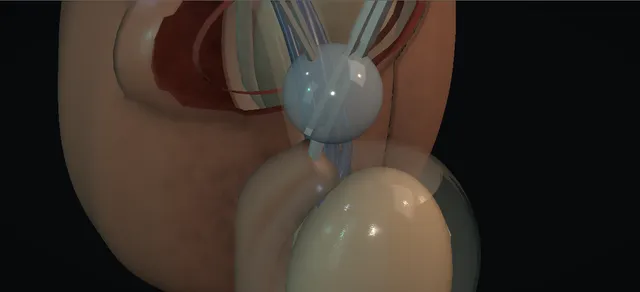
Epididymal cyst excision
Testis delivered, cyst dissected off the head of the epididymis to its neck, tied clear of the upper pole. Epididymectomy as a second path.
Genital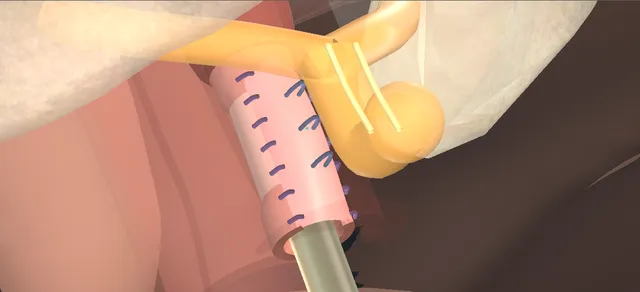
Female urethroplasty
A dorsal onlay buccal graft: the plane opened under the clitoris, the roof cut at twelve into healthy urethra, the graft sewn in and quilted.
Continence + urethra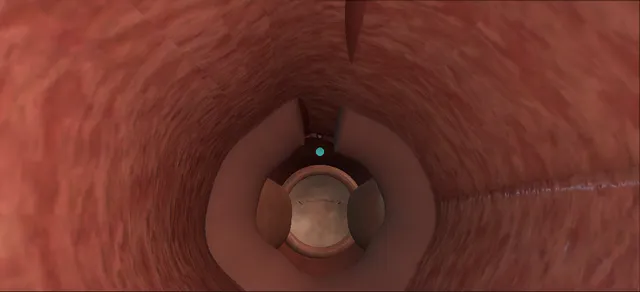
External sphincterotomy
Detrusor sphincter dyssynergia after spinal injury: one twelve o’clock cut through the full sphincter, the ring opening, and a sheath catheter after.
Continence + urethra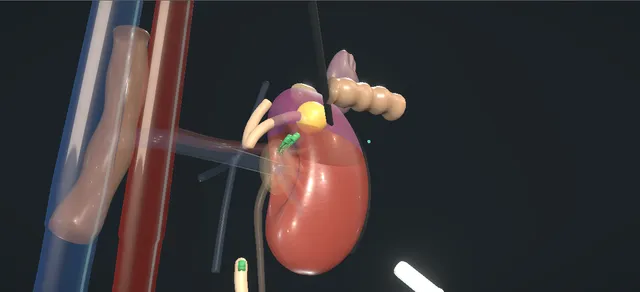
Paediatric nephrectomy and heminephrectomy
A non-functioning kidney out through three small ports: the ureter to the hilum, small vessels clipped. Then an upper-pole heminephrectomy with the lower pole kept.
Paediatric
Testicular prosthesis
A high scrotal incision, a dependent pouch to the bottom, the implant stitched by its loop and the neck closed above it. Too small a pouch rides high.
Genital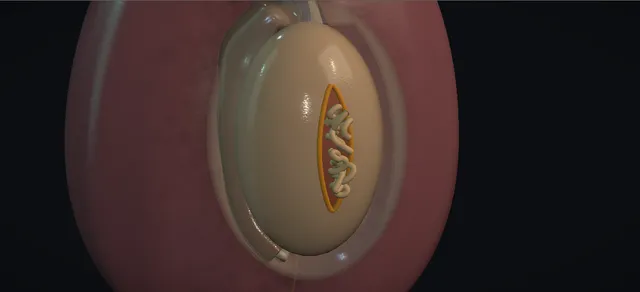
Scrotal trauma: exploration
A ruptured testis after a blunt blow: the scan, the haematocele evacuated, extruded tubules trimmed and the tunica albuginea closed. Explore early.
Genital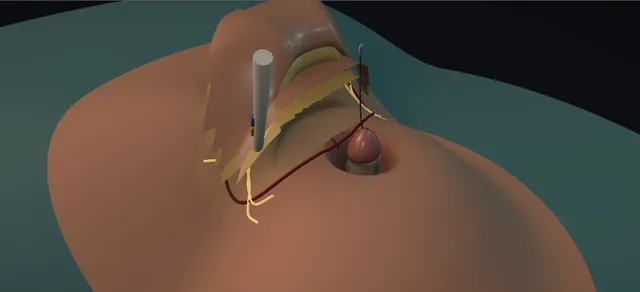
Adult acquired buried penis
A normal-length shaft buried under a pannus: cicatrix release, escutcheonectomy, excision of scarred skin, base fixation and a quilted split skin graft.
Genital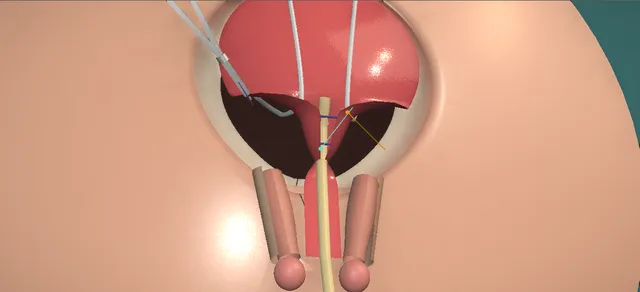
Bladder exstrophy repair
Primary closure in the modern staged repair: the plate freed, the outlet tubularised, the bladder closed and dropped, the pubis brought together after osteotomy.
Paediatric
Paediatric stone procedures
Ultrasound first, the route by size and site, then a mini-PCNL: one small tract, the laser and the washout; ureteroscopy for the lower ureter.
Paediatric
Fournier gangrene: debridement
Excise to bleeding tissue past where the skin looks dead, keep the testes, urethra and sphincter, pack, look again, then pouches and a graft.
Emergency + trauma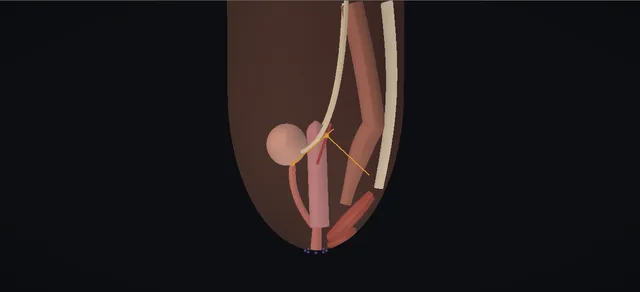
Cloacal reconstruction
One perineal opening: decompression, the channel measured, the rectum separated, urethra and vagina brought down as one block, three openings.
Paediatric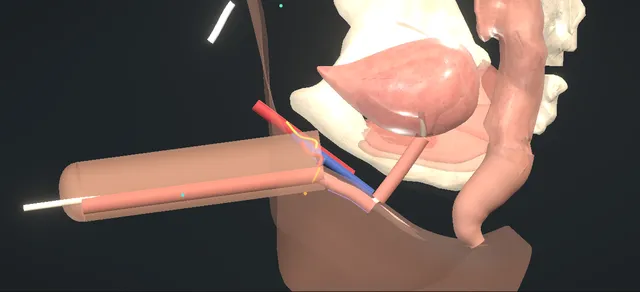
Masculinising urogenital reconstruction
Radial forearm phalloplasty: the pars fixa tubed over a catheter, a tube within a tube, and the join where fistula and stricture start.
Genital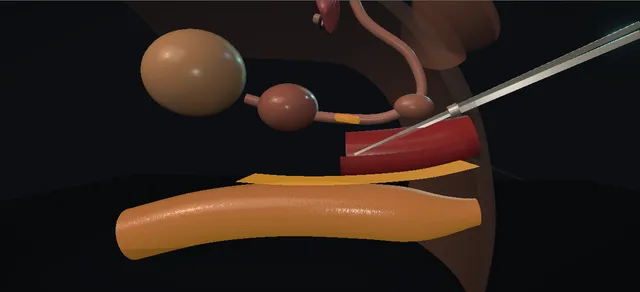
Penile inversion vaginoplasty
Orchidectomy, the space between prostate and rectum, a neoclitoris on the dorsal bundle, the urethra spatulated to a new meatus and the skin tube inverted.
GenitalNo animations match your search.
Explore by anatomy
Start with an organ.
Know the first three moves.
Model. Mechanism. Save. Viva answer.
Explore the cards ↗ For departmentsBring it into your teaching.
Use the atlas for case preparation and debriefs.
Explore a collaboration ↗