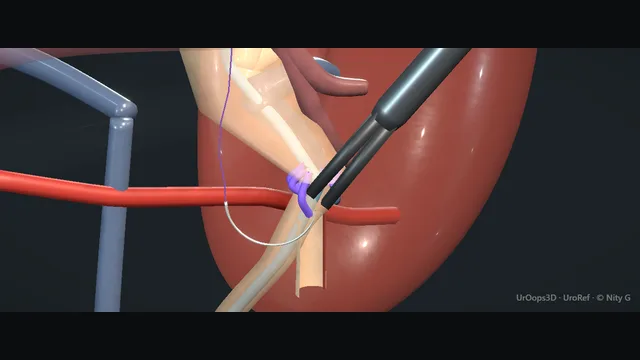
A laparoscopic transperitoneal left pyeloplasty, from colon reflection to a stented anastomosis.
The case is decided by one relationship: a lower-pole vessel crossing in front of the junction, and the operation is the re-route of the junction in front of it, leaving the vessel behind the repair.
Advanced tierFRCS reconstruction, PUJ obstructionInteractive 3D
The ureteropelvic junction and the vessel crossing in front of it. Schematic, not to scale; relationships only.
The scene is one relationship: a vessel off the aorta crossing in front of the ureteropelvic junction, a pelvis ballooned above it and a ureter collapsed below.
The operation re-routes the junction in front of the vessel and rebuilds it wide, over a stent, without tension.
›Renal pelvis - ballooned and often redundant in crossing-vessel obstruction; trimmed to a funnel, not left as a reservoir.
›Lower-pole crossing vessel - an artery, sometimes with a vein, from the aorta or renal artery passing anterior to the PUJ; preserved and bypassed.
›PUJ (the narrow segment) - the intrinsic dysmotile segment, often adherent to the vessel; excised, not dilated.
›Ureter + spatulation - spatulated laterally so the anastomosis matures wide; the distal ureter is identified before any division.
›JJ stent - sits across the anastomosis draining the pelvis while it heals; removed on imaging, not on the calendar alone.
Exposure + colon reflectionTransperitoneal access is gained with the patient rolled. The left colon is reflected medially off the kidney in the plane beneath its mesentery until the ballooned pelvis and the hilum are fully exposed. The ureter is identified first, distal to the obstruction where it is normal calibre, and followed up to the junction before anything is divided. An under-reflected colon leaves the whole case cramped for angle, so the reflection is completed before the dissection of the junction starts. Identifying the ureter below before mobilising the pelvis above is the check that keeps the wrong structure from being divided. where it bites: operating on a hugely distended pelvis without first seeing the ureter below it is how the wrong structure gets injured.
Identify the crossing vesselThe PUJ is mobilised completely, the pelvis lifted off its bed and the tissues anterior to the junction cleared until the whole crossing relationship is visible. A lower-pole vessel crossing anterior to the junction, with a ballooned pelvis above and a collapsed ureter below, is the cause, and the geometry itself is the confirmation. The vessel is preserved and the junction is moved behind it, never the vessel divided, because division sacrifices functioning lower-pole parenchyma. Mobilisation also finds the segmental branches that hide behind a distended pelvis, and it finds them before the pelvis is divided, not into it. where it bites: an aberrant vessel is not always the cause; divide nothing until the whole junction is mobilised and the true narrow segment is seen.
Dismember + spatulateThe pelvis is transected above the narrow segment, the dysmotile segment is excised in full, and a redundant pelvis is trimmed until what remains funnels down to the anastomosis. The ureter is spatulated laterally, on the side away from the vessel, so the widest part of the new mouth faces the drainage angle. A short spatulation with a redundant pelvis left behind is the setup for a stenosing, stagnant anastomosis. Both errors look tidy at the end of the case and declare themselves later as failed drainage. where it bites: a short spatulation with a redundant pelvis left behind is the setup for a stenosing, stagnant anastomosis.
Transposition anterior to the vesselWhen a crossing vessel is preserved, the spatulated ureter is brought in front of it before the first suture is placed, so the new junction lies anterior to the vessel and the vessel runs behind the repair. The transposition is checked on the table by running the ureter and the vessel in view: no crossing anterior to the repair, no kink where the ureter passes in front. The anastomosis is then built around that geometry, dependent end first. Rebuilding the junction behind the vessel recreates the exact obstruction that brought the patient to theatre, and it does so behind a technically perfect suture line. where it bites: rebuilding the junction behind the vessel recreates the obstruction that brought the patient to theatre.
Anastomosis + stentThe anastomosis is run as a tension-free, mucosa-to-mucosa suture line, widest where the ureter was spatulated and tapering into the pelvis as a funnel. The posterior row goes in first, while the anterior wall is still open; the wire and then the JJ stent are passed across the open join, the lower coil down to the bladder, and the anterior row closes over the stent. A JJ stent is passed over a wire across the anastomosis before the final sutures are placed. Position is confirmed so the stent drains the pelvis rather than the pararenal space. Sutures are spaced to close the join without gathering it, because a watertight anastomosis built under tension fails as either a leak or a stricture. where it bites: suturing under tension, or closing without the stent correctly across, produces the leak or the obstruction.
Drainage + closureA drain is laid near the anastomosis before the colon is allowed to fall back, positioned so a leak declares itself in the drain rather than as a collection. Most drains do nothing, and that is the point: a dry drain is reassurance, a drain that fills has given the answer on the first day. The stent is booked for removal against imaging that confirms free drainage, not against the calendar alone. The op note records the vessel findings, the anastomosis and the stent position, because the follow-up plan is built on what the operation actually found.
The spatial relationships the animation is built to make automatic. Before you read each one, ask yourself: at this point in the operation, what is about to go wrong, and what is my first move? The save for each sits in the Complications tab.
RiskCrossing vessel anterior to the PUJ - the cause in most vascular obstructions; injured during mobilisation, it bleeds at the hilum.
RiskHigh-riding medial vessels during dismembering - segmental branches can hide behind a ballooned pelvis; the pelvis is fully mobilised before it is divided.
RiskAnastomotic tension - a ureter left short or a pelvis under-mobilised pulls at the suture line; tension is the mechanism of both leak and stenosis.
When the case turns: the problem, then the next move.
ActionBleeding obscures the vessel window - pressure and patience: raise insufflation, pack with a gauze roll, irrigate, and return to a dry field before any clip is placed.
ActionStent will not pass distally - check the wire is in the ureter and not submucosal; use a stiffer wire and rotate the stent, and if it still will not pass, drain with a nephrostomy and re-stent later.
ActionPelvis much larger than expected - trim the redundant pelvis and taper it into the anastomosis; a left-behind reservoir causes stasis, not relief.
ActionUreter too short for a tension-free join - mobilise the kidney fully and bring it down; a downward nephropexy buys length where transposition alone does not.
The examiner stems this scene prepares you for. Try to answer out loud first, then reveal, and learn the discriminator, the detail that turns a pass into a strong pass.
QA crossing vessel is found anterior to the PUJ during a dismembered pyeloplasty. How does it change the operation?reveal answer
The vessel is the reason the dismembered repair is chosen, and it is preserved, not divided.
Once the junction is fully mobilised, the vessel is seen crossing anterior to the PUJ, typically a lower-pole segmental artery arising early from the renal artery or the aorta, with a ballooned pelvis above and a normal-calibre ureter below.
Dividing it sacrifices functioning lower-pole parenchyma, so the standard approach is transposition: the pelvis is dismembered above and the ureter below the obstruction, the narrow segment excised, the ureter spatulated laterally, and the new anastomosis built with the ureter brought in front of the vessel.
The new junction then lies anterior to the vessel, which runs behind the repair.
Division is reserved for exceptional cases, for example a small accessory vessel supplying minimal parenchyma, or anatomy that defeats transposition, and it is a deliberate consultant-level decision made with the supply of the lower pole in view, never an improvisation during bleeding.
Strong pass
Say all three
Transposition in front of the preserved vessel
Plus the lateral spatulation
Named as the two moves that keep the new junction off the vessel bed
Examiner note
Transposition in front of the preserved vessel, plus the lateral spatulation, named as the two moves that keep the new junction off the vessel bed.
QLaparoscopic pyeloplasty, open pyeloplasty or endopyelotomy: how do you choose?reveal answer
The dismembered pyeloplasty is the reference repair because it removes the dysmotile segment, reduces a redundant pelvis and deals with crossing vessels;
its success is the highest of the three and it is the operation the others are measured against.
Endopyelotomy has lower and less durable success, and it performs worst exactly where the dismembered repair performs best: crossing vessels, a very large pelvis and poor differential function are relative contraindications to it.
It is reserved for selected patients, such as secondary strictures after previous reconstruction in a patient unfit for a full repair, where a percutaneous or endoscopic incision is a reasonable lesser procedure.
Laparoscopic and robotic approaches reproduce the open operation with less pain and a shorter stay, at the cost of operative time and equipment;
open pyeloplasty remains defensible for complex redo surgery and where minimally invasive capacity is unavailable.
The decision runs: function and anatomy first, crossing vessel and pelvis size against endopyelotomy, then approach by resource and expertise.
Strong pass
Say all three
Naming crossing vessel
Pelvis size and differential function as the variables that exclude endopyelotomy
Framing the dismembered repair as the standard the alternatives must justify themselves against
Examiner note
Naming crossing vessel, pelvis size and differential function as the variables that exclude endopyelotomy, and framing the dismembered repair as the standard the alternatives must justify themselves against.
QHow is an anastomotic leak prevented after pyeloplasty, and how is a leak managed when it happens?reveal answer
Prevention is technical and mechanical: excise the dysmotile segment entirely, spatulate the ureter laterally so the join is widest at the drainage angle, trim the redundant pelvis into a funnel, and close healthy, well-perfused edges over a correctly placed JJ stent without tension, with a drain nearby.
A tension-free mucosa-to-mucosa anastomosis over a stent prevents the great majority of leaks.
When a leak occurs, management is drainage rather than re-operation: confirm the stent lies across the anastomosis and is patent, keep the surgical drain until output settles, and culture and treat urine as indicated.
Ultrasound or CT defines any urinoma, and a significant or symptomatic collection is drained percutaneously.
Return to theatre is reserved for the septic patient, the failed drain or a collection that cannot be controlled radiologically.
Most leaks close on drainage within days; persistence beyond that raises the question of distal obstruction or a disrupted anastomosis, and that patient needs imaging and a consultant plan, not patience alone.
Strong pass
Prevention named as tension plus stenting plus trimming, and management framed as drainage-first with re-operation reserved, not the reverse.
QSix weeks after pyeloplasty the patient has pain and the kidney looks more dilated. Work-up and plan?reveal answer
The first check is the stent: confirm it is present, correctly positioned and patent, because a migrated stent is the commonest remediable cause at this interval.
Then define whether the pelvis is obstructed or merely decompensated: ultrasound or CT defines the anatomy, and a diuretic renogram defines function and drainage, separating true obstruction from a flaccid, chronically dilated system that remodels over months.
Exclude and treat infection, which both causes pain and prejudices the anastomosis.
If obstruction is confirmed, decompress: a nephrostomy with an antegrade study shows the level and calibre of the narrowing, and simple oedema at the anastomosis settles with a further period of stenting.
A fibrotic stricture that fails a reasonable period of drainage needs redo reconstruction, with endopyelotomy as a weaker alternative, and the patient should have been counselled from the outset that a minority of pyeloplasties need revision.
Strong pass
Say both
Excluding stent migration before blaming the anastomosis
Using functional imaging to separate obstruction from a capacious system that is draining adequately
Examiner note
Excluding stent migration before blaming the anastomosis, then using functional imaging to separate obstruction from a capacious system that is draining adequately.
Say it aloud, then reveal. Reading is not remembering.
01The relationshipSay the critical spatial relationship out loud, then reveal.reveal
Memory frame
The scene is one relationship: a vessel off the aorta crossing in front of the ureteropelvic junction, a pelvis ballooned above it and a ureter collapsed below.
Why?
The operation re-routes the junction in front of the vessel and rebuilds it wide, over a stent, without tension.
02The first moveCrossing-vessel injury. Your first move?reveal
First move
Stop dissecting and compress the bleeding point with a gauze roll or suction tamponade; do not clip blind into the hilum.
03The escalation triggerCrossing-vessel injury. What makes you call for help?reveal
Escalate when
Uncontrolled hilar bleeding or a failing patient → convert to open with proximal control first, and involve vascular surgery early.
04The discriminatorWhat turns a pass into a strong pass?reveal
Strong pass
Say all three
Transposition in front of the preserved vessel
Plus the lateral spatulation
Named as the two moves that keep the new junction off the vessel bed
Examiner note
Transposition in front of the preserved vessel, plus the lateral spatulation, named as the two moves that keep the new junction off the vessel bed.
05The pitfallWhere does this operation bite first?reveal
Pitfall
Crossing vessel anterior to the PUJ
Why?
the cause in most vascular obstructions; injured during mobilisation, it bleeds at the hilum.
Revision practice with self-marked answers, not an assessment of clinical competence. Kept in
this browser only; it does not sync between devices.