
Revision sheet
Emergency scrotal exploration: torsion
6 steps, each one the authored title and caption from the interactive animation, with the frame captured from that step. Read it before the case, or print it and work through the steps in order.
Teaching only, not for diagnosis or treatment decisions. The text on this sheet is the animation's own step copy, reproduced verbatim.
UrOops3D · UroRef · © Nity G
- 01
The clinical picture
- Sudden severe pain, vomiting, a high-riding testis lying transversely, an absent cremasteric reflex.
- The diagnosis is clinical, time is tissue, and the salvage window is about six hours.
- 02
Scrotal incision
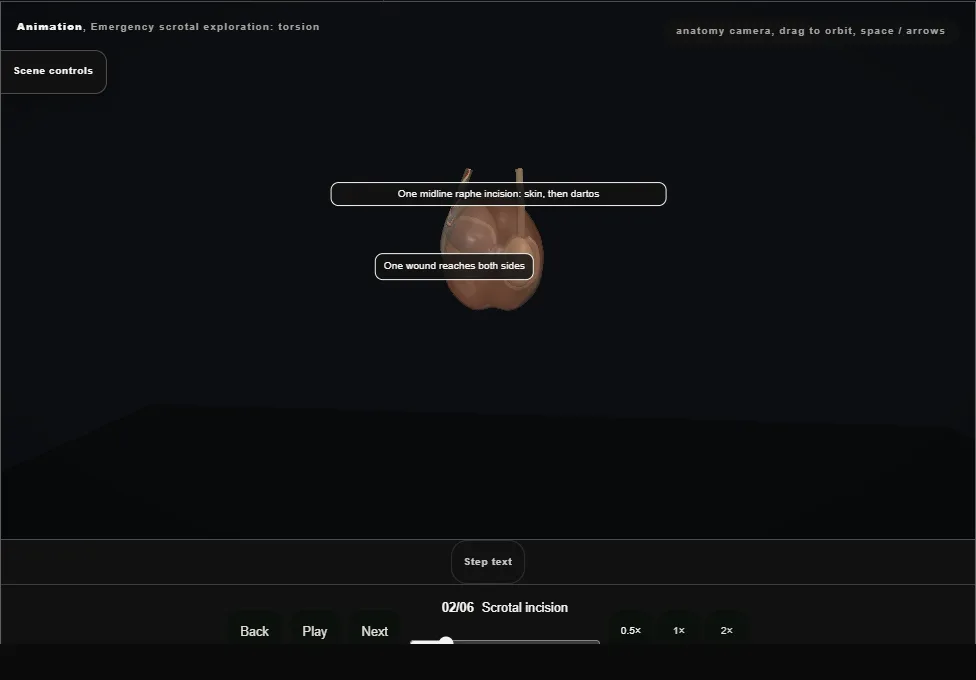
- A single midline raphe incision reaches both hemiscrota through one wound: skin, dartos, and each tunica in turn.
- 03
Delivery + derotation
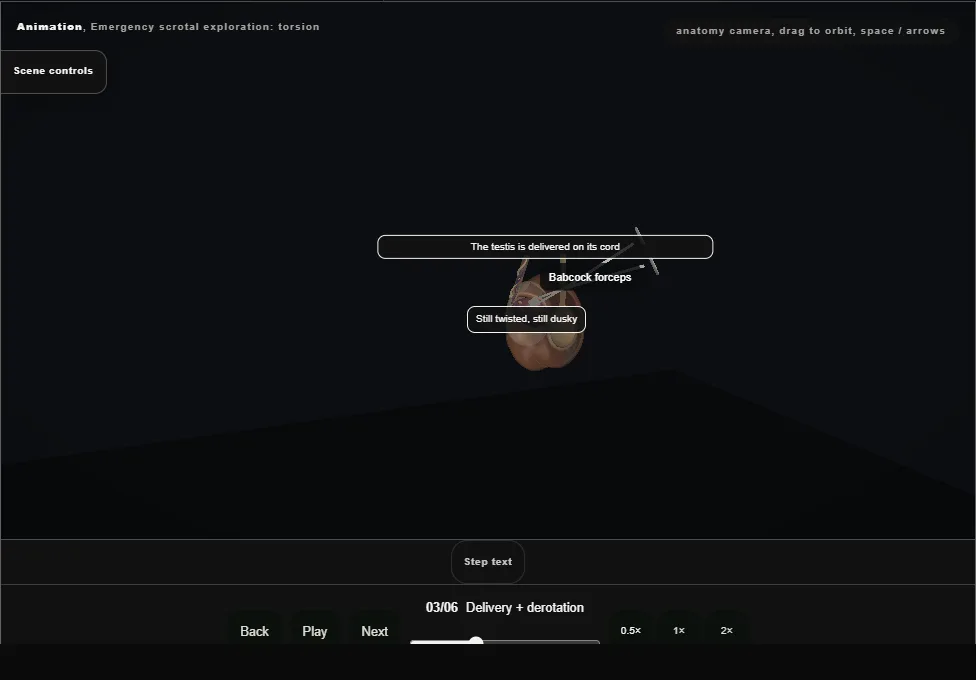
- The affected testis is delivered and untwisted outward, like opening a book.
- For a left torsion this is clockwise, and for a right torsion counter-clockwise, viewed from the foot of the table; reverse direction if the cord tightens.
- 04
Wait, fix the other side, reassess
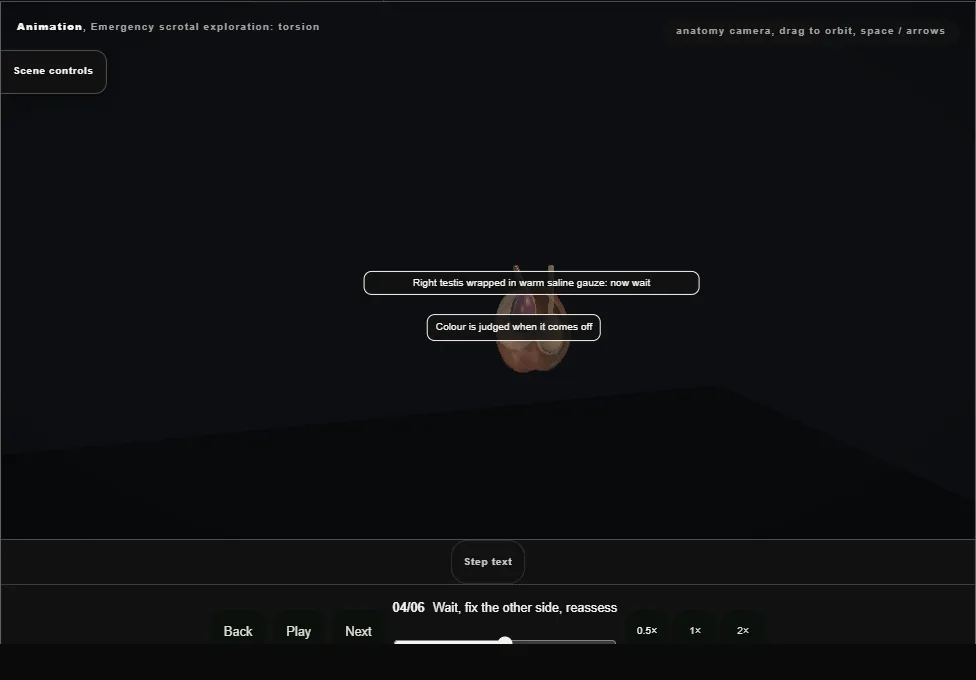
- After derotation, wrap the testis in warm saline gauze and wait.
- During the wait the other testis is fixed at three points through the same wound.
- Then the gauze comes off and colour and capillary bleeding are reassessed.
- Only if viability remains uncertain is a small tunica albuginea nick used to look for fresh bleeding.
- 05
Orchidectomy only if unequivocally non-viable
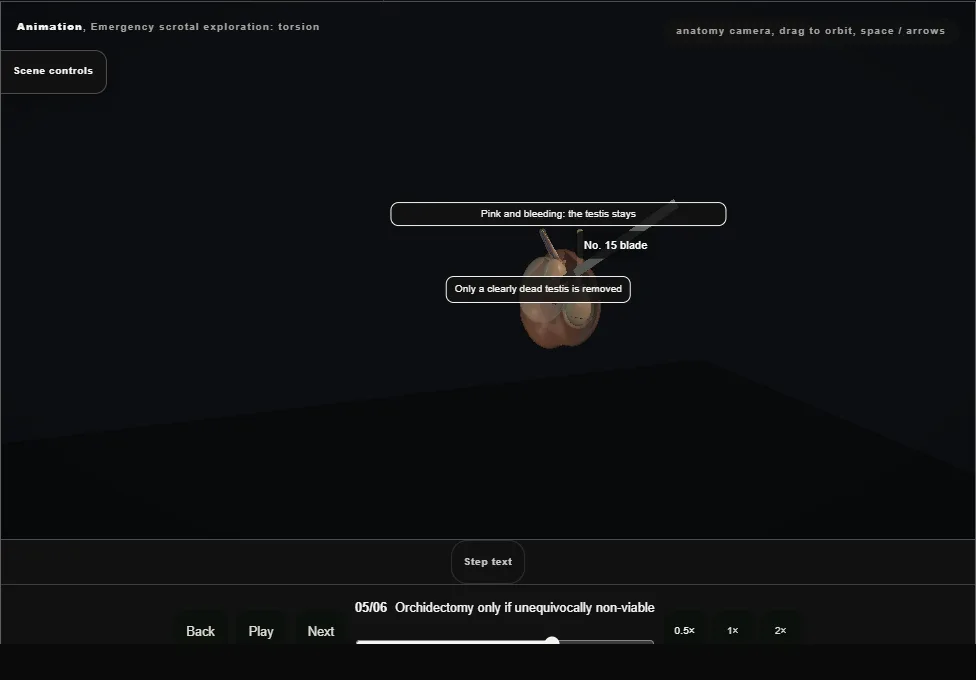
- Only an unequivocally non-viable testis is removed: cord clamped, ligated and divided.
- A dusky testis of uncertain viability is replaced and followed rather than removed by an absolute colour rule.
- 06
Fixation of the affected testis
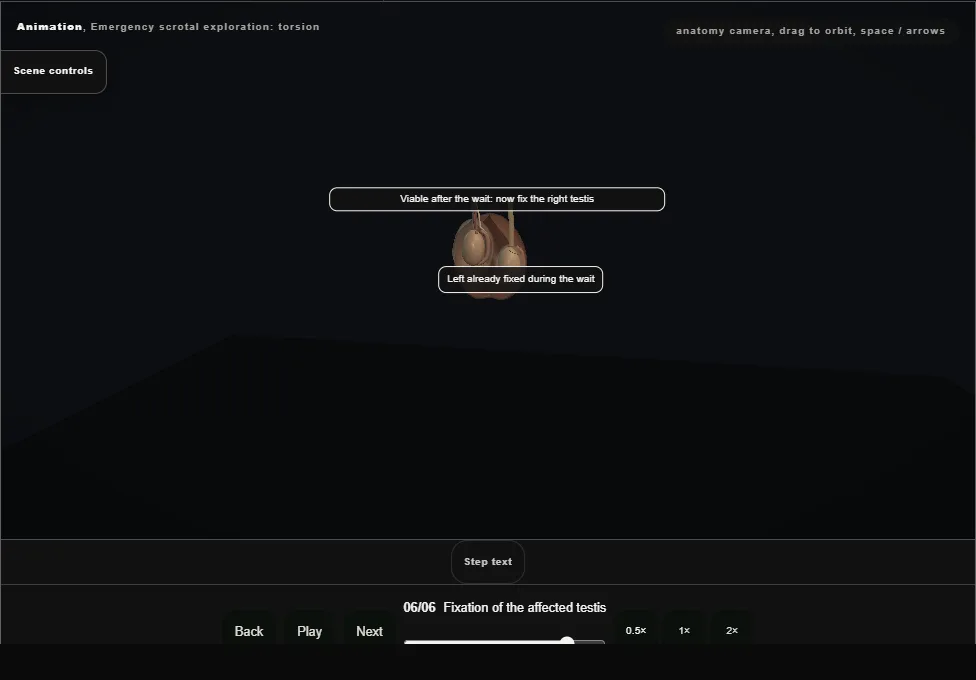
- Viable on reassessment, the affected testis now gets three-point fixation to the scrotal wall.
- The other testis was already fixed during the warm-gauze wait, so with a bell-clapper anomaly both end fixed; after orchidectomy, that fixation protects the contralateral testis.
Derived from TorsionScene.tsx at build time: every step title and caption above is the authored
ProcedureDef text, reproduced verbatim, and this page shares its readable-points renderer with the animation
itself. 6 of 6 steps have a captured frame.
Text fingerprint d331c960307c3175. A caption edit without a re-capture fails the production
check, so the sheet and the animation cannot drift apart silently.