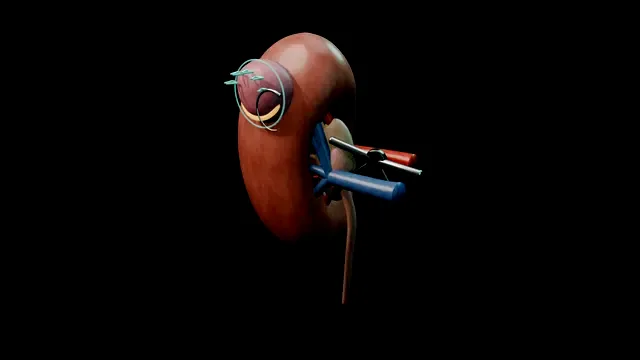
A clamp, a clock and two suture layers. The tumour leaves with a thin visible rim while the kidney is pale; the inner layer closes the collecting system, the outer layer holds the haemostasis, and the colour comes back only when both are done.
Advanced tierFRCS uro-oncology, renal surgeryInteractive 3D
Through an exophytic tumour into the kidney, surface to base. Schematic, not to scale; relationships only.
Deep to an exophytic tumour lie, in order: the parenchymal rim you take, the calyces you close, the segmental vessels you stitch, and the capsule you re-approximate.
The clamp decides how long you have to respect that stack.
›Renal artery - clamped for warm ischaemia; the length of clamp time trades directly against nephron mass.
›Tumour + rim - the excision carries a visible rim of normal parenchyma; enucleation alone is selected case by case.
›Collecting system - entered for deep tumours; the inner suture layer closes it watertight.
›Renorrhaphy layers - inner for the base, outer for the capsule; each layer has its own failure mode.
Read the modelCross-sectional imaging is read before the patient reaches the table: endophytic depth, distance from the collecting system, and which segmental arteries supply the tumour. From that read the excision line is drawn, the number and position of bulldogs is chosen, and the order of the reconstruction is fixed. The check is that the whole team can state the plan back: which artery, which rim, which suture first. Discovering the arterial anatomy after the clamp is on is the error this step exists to prevent, because surprises inside the clamp interval are paid for in ischaemia time.
Hilum exposed + artery slungAfter colon reflection the arterial side of the hilum is opened and the artery skeletonised over enough length that a bulldog sits flat, without rotation or tension on the vessel. Where the arterial map shows a single segmental supply to the tumour, that branch is prepared instead for selective clamping. The vein is identified and its course known, but left flowing in the usual case, because venous congestion adds to parenchymal bleeding when the clamp comes off. The check before moving on is that the bulldog can be applied and released in one clean movement, without repositioning, because fumbling at the artery burns clock time that belongs to the excision.
Clamp + excisionThe bulldog closes, the kidney pales to a uniform colour, and the warm ischaemia clock is called aloud and recorded. Excision proceeds with cold scissors around the marked rim, staying in a thin shell of normal parenchyma and avoiding diathermy charring that would burn the margin the pathologist has to read. The bed is inspected as it opens, with sinus fat, calyces and segmental vessels named to the assistant as they are met, so nothing is closed blind later. The discipline this step teaches is that the reconstruction is rehearsed before clamping, because every minute spent deciding under the clamp is nephron lost. where it bites: every minute of clamp time is nephron loss; the reconstruction is rehearsed before clamping, not improvised after.
Inner layerThe inner layer is a running absorbable stitch through the parenchymal edge that closes every opened calyx and any vessel visible in the base of the defect. It is run systematically from one end of the repair to the other rather than picked at point to point, so no calyx is skipped because it happened to look dry. A dry field under arterial occlusion is not proof of a sealed system: a calyx never sutured will leak again once flow returns. This layer, placed under clamp, is the actual urine-leak prevention; the outer layer is haemostasis, and the two are not interchangeable. where it bites: a missed calyx is a urinoma on day three.
Outer layerThe outer layer is a row of capped sutures on sliding clips, each passed through capsule and cortex on both sides of the defect and tensioned until the edges meet over the bolster. Each clip is adjusted in turn so compression is even along the whole repair, rather than one point strangling while its neighbour sits loose. The tension is set deliberately a shade loose with the clamp still on, because the kidney swells when perfusion returns and a repair tensioned to the empty kidney cuts through on reperfusion. Compression, not cautery, is what keeps the bed dry in the hours after theatre.
Reperfusion + checkThe bulldog comes off and reperfusion is watched directly: colour returns across the kidney and the repair takes arterial pressure for the first time. Capillary ooze is given a patient minute to settle, with the bed held exposed rather than packed away. Anything pulsatile, or any welling that re-accumulates after suction, receives a targeted stitch there and then, with re-clamping if the point cannot be controlled off-clamp. The field is left only when the repair is dry, the clamp time is recorded, and the drain position relative to the suture line is confirmed.
The spatial relationships the animation is built to make automatic. Before you read each one, ask yourself: at this point in the operation, what is about to go wrong, and what is my first move? The save for each sits in the Complications tab.
RiskWarm ischaemia clock - clamp time is nephron loss; the target is under 25 minutes, and every minute under the clamp is planned before it starts.
RiskThe tumour base - where margin, calyx and artery meet; haste here produces all three complications at once.
RiskSegmental vessels in the bed - a slipped stitch is a delayed pseudoaneurysm presenting as gross haematuria at home.
Trigger each of these live in the Animation tab, then read the save: the first move, the escalation trigger, and the line that goes in the op note.
Positive surgical margin
histology shows tumour at the inked edge; the risk lives in the moment of excision.
The save
Intra-operatively: excise with a visible rim of normal parenchyma; inspect the bed before closing.first move
Use frozen section on the base where depth is uncertain and the facility exists.
A positive margin is usually a surveillance and MDT conversation, not an immediate re-operation.
Re-discuss at the MDT: options range from imaging surveillance to completion nephrectomy depending on histology, margin type and renal reserve.escalation trigger
Op note: depth of excision, rim appearances, frozen section result, and the explicit margin plan communicated to the patient.document
Urine leak / urinoma
a calyx entered and not closed drains into the retroperitoneum.
The save
Recognise it: drain output that is high, persistent or smells of urine; new flank pain or ileus.first move
Send drain fluid for creatinine - a level at serum-multiples confirms urine.
Keep the drain in situ as the controlled fistula; most leaks close with drainage and time.
Persistent leak: imaging (CT or nuclear) to define the collection, percutaneous drainage of any urinoma, and consider a JJ stent to decompress the system.escalation trigger
Op note: calyx entered and closed (or not), drain placed, leak plan and imaging follow-up.document
Delayed bleed / pseudoaneurysm
gross haematuria days after an uneventful operation: a segmental artery pseudoaneurysm until proven otherwise.
The save
Do not reassure it away: delayed gross haematuria after partial nephrectomy is an angiography question.first move
Resuscitate as needed: bed rest, catheter with irrigation if clot retention, cross-match.
CT angiography defines the lesion; selective angioembolisation is both diagnosis and treatment.
Haemodynamic instability with failed embolisation or a ruptured pseudoaneurysm → theatre for haemostasis, accepting that nephrectomy may be the price.escalation trigger
Op note: clamp time, bed vessels stitched, embolisation performed, renal function trajectory.document
When the case turns: the problem, then the next move.
ActionBulldog will not hold on the artery - check for accessory arteries on the pre-op map; two clamps beat one leaky one.
ActionTumour deeper than the model suggested - convert from excision to partial amputation (wedge) planning the collecting-system closure first.
ActionBleeding on reperfusion from the bed - re-clamp, one more targeted stitch over the point, then release; pressure alone rarely holds an arterial point.
ActionClamp time running past plan - finish the inner layer, release early if the outer layer can be completed off-clamp with sliding clips.
The examiner stems this scene prepares you for. Try to answer out loud first, then reveal, and learn the discriminator, the detail that turns a pass into a strong pass.
QHow do you minimise nephron loss during clamping?reveal answer
Preparation before the clamp is the main lever: full mobilisation, tumour mapping, suture readiness and a rehearsed order of reconstruction, so the clamp interval contains only the steps that need an avascular field.
Then technique: selective (branch) clamping where the arterial map allows it, early unclamping once the inner layer is secure, and off-clamp completion of the outer layer where feasible.
Every centre works to a warm ischaemia threshold, commonly taught as keeping clamp time as short as possible with a target of under 25 minutes, and the deep principle is that a kidney saved from ischaemia but left leaking or bleeding has not been spared at all.
Strong pass
Say both
Naming preparation and selective clamping as the levers
Being precise that thresholds are centre-defined rather than quoting a single hard number as gospel
Examiner note
Naming preparation and selective clamping as the levers, and being precise that thresholds are centre-defined rather than quoting a single hard number as gospel.
QEnucleation versus excision with a rim: when is each acceptable?reveal answer
Standard partial nephrectomy excises the tumour with a visible rim of normal parenchyma, which gives the safest margin for the majority of renal tumours.
Enucleation along the tumour pseudo-capsule is accepted in selected settings: hereditary syndromes with multiple tumours, imperative indications such as a solitary kidney where parenchyma is precious, and some exophytic small tumours where the plane is clean and frozen section is available.
The trade is maximal parenchymal preservation against a higher risk of a positive margin when the pseudo-capsule is breached.
The MDT, the imaging and the renal reserve make that decision before the table, not on it.
Strong pass
Tying the choice to imperative indications and hereditary multifocal disease rather than presenting enucleation as a general shortcut.
QYour drain is putting out 400 ml a day of clear fluid on day 3. What is it and what do you do?reveal answer
After partial nephrectomy that is a urine leak until proven otherwise, and drain fluid creatinine compared with serum confirms it.
I would keep the drain as the controlled output rather than removing it, image the kidney to define the leak and any urinoma, and exclude obstruction distally.
Most leaks close with continued drainage over days to weeks as the inner layer seals.
If output persists or a urinoma forms, I would place a JJ stent to decompress the collecting system and drain the collection percutaneously, and re-image on a planned schedule.
Failure to progress after a reasonable interval brings re-exploration or nephrectomy into the discussion, but the vast majority never get there.
Strong pass
Say all three
Confirming with drain creatinine
Keeping the drain in as management
Not removing it to make the number look better
Examiner note
Confirming with drain creatinine and keeping the drain in as management, not removing it to make the number look better.
QWhat features on imaging make a tumour suitable for nephron-sparing surgery?reveal answer
Size first: T1a and a growing proportion of T1b tumours.
Then anatomy: exophytic rather than endophytic growth, a location away from the hilum and collecting system on depth scoring, and a renal score that summarises those variables for planning.
Patient factors push the same direction: chronic kidney disease, a solitary or contralaterally threatened kidney, bilateral tumours, or syndromes with multifocality.
Conversely, locally advanced disease, renal vein involvement, an unfavourable central location with no achievable margin, or a patient whose comorbidity makes a long warm-ischaemia operation dangerous all argue for radical nephrectomy.
The scoring systems support the decision; they do not make it alone.
Strong pass
Say both
Naming endophytic depth and hilar proximity as the anatomical limiters
Patient comorbidity as a genuine factor in the operative trade
Examiner note
Naming endophytic depth and hilar proximity as the anatomical limiters, and patient comorbidity as a genuine factor in the operative trade.
Say it aloud, then reveal. Reading is not remembering.
01The relationshipSay the critical spatial relationship out loud, then reveal.reveal
Memory frame
Deep to an exophytic tumour lie, in order
Why?
Deep to an exophytic tumour lie, in order: the parenchymal rim you take, the calyces you close, the segmental vessels you stitch, and the capsule you re-approximate. The clamp decides how long you have to respect that stack.
02The first movePositive surgical margin. Your first move?reveal
First move
Intra-operatively: excise with a visible rim of normal parenchyma; inspect the bed before closing.
03The escalation triggerPositive surgical margin. What makes you call for help?reveal
Escalate when
Re-discuss at the MDT: options range from imaging surveillance to completion nephrectomy depending on histology, margin type and renal reserve.
04The discriminatorWhat turns a pass into a strong pass?reveal
Strong pass
Say both
Naming preparation and selective clamping as the levers
Being precise that thresholds are centre-defined rather than quoting a single hard number as gospel
Examiner note
Naming preparation and selective clamping as the levers, and being precise that thresholds are centre-defined rather than quoting a single hard number as gospel.
05The pitfallWhere does this operation bite first?reveal
Pitfall
Warm ischaemia clock
Why?
clamp time is nephron loss; the target is under 25 minutes, and every minute under the clamp is planned before it starts.
Revision practice with self-marked answers, not an assessment of clinical competence. Kept in
this browser only; it does not sync between devices.