
Intradetrusor botulinum toxin injection
Cystoscopic injection into the bladder wall for selected refractory overactive or neurogenic detrusor dysfunction, with retention and infection central to consent.
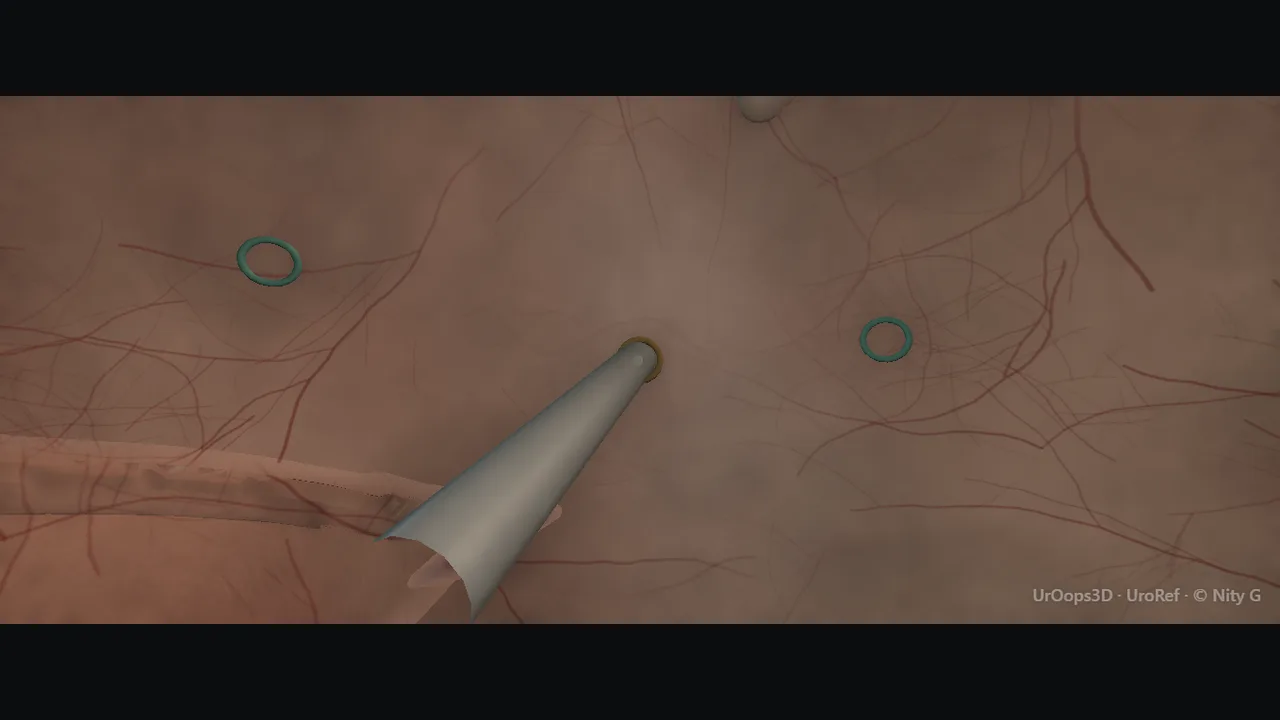 Interactive 3D Interactive operative model Open the 3D animation
Teaching catalogue only. This coverage record is not a patient pathway or operative instruction.
Typical place in practice
Persistent urgency incontinence or neurogenic detrusor overactivity after assessment and discussion of catheterisation capability.
Alternatives and neighbouring procedures
Behavioural and pharmacological treatment, neuromodulation, catheter strategies or reconstructive surgery in selected severe disease.
Same procedure family, explicit technique branches
These are variations of this canonical operation. Complication modules below identify whether they apply to all branches or only to named approaches.
Idiopathic overactive-bladder injection pattern
Targets the bladder wall using a standardised local protocol for non-neurogenic symptoms.
Neurogenic detrusor-overactivity pattern
Uses a condition-specific protocol with upper-tract protection and catheter planning.
Repeat injection
Repeats treatment when benefit wanes after reassessment.
High-level sequence
Coverage outline only; not a step-by-step technical guide.
- Confirm indication, urine status and ability to manage retention
- Inspect the bladder
- Create evenly distributed controlled intradetrusor deposits
- Complete haemostasis and drainage assessment
- Monitor emptying, infection and symptom response
Operative notes
Concise operative notes covering the key steps, landmarks and watch points, in the order you encounter them.
Functional bladder surgery
What it does: rebuild or control a difficult bladder.
Augmentation (ileocystoplasty)
- 20-25 cm ileum, opened along its far border.
- Bladder split front to back. The halves must not pull together again.
- Patch sewn in, 2 running 3/0 threads.
- Supra + urethral catheters + drain.
- Washouts 3x a day, against mucus.
- Supra out day 13. Urethral day 14. Cystogram if any doubt.
Detrusor myectomy
- Blue dye in the bladder.
- Inverted-U muscle cut over the dome.
- Muscle peeled OFF the lining underneath.
- Hole in the lining ~50%. Close 6/0. Drain.
- Never over-fill after.
Artificial sphincter (AUS)
- Obsession with clean technique. Minimal traffic. Double gloves. Wash the field.
- Bulbar cuff after prostate surgery. Bladder neck cuff: women, children, catheterisers.
- ContiClassic balloon 60-69 (bulbar) or 70-79 (neck) cmH2O. Redo for wear: higher balloon, or cuff 0.5 cm smaller. Irradiated: lower balloon.
- Pump in a dependent scrotal pouch in front of the LEFT testis. Button forward.
- Off for 6 weeks. Activate in clinic. Teach cycling.
- 2026 update: Device by approach: Rigicon ContiClassic for the perineal incision, AMS 800 for the penoscrotal. Erosion 3-10%. Infection 1-5%.
- 2026 update: Penoscrotal approach: before the incision, pull the shaft straight up off the scrotum. Hold it on the pubic region with a stay stitch through the glans.
- 2026 update: Sacral neuromodulation: 2 stages. Test wire. Over 50% better on a diary = permanent wire.
- 2026 update: Botox 100 U in 10 mL: 20 x 0.5 mL, into the bladder wall, spare the trigone. Effect 6-9 months. Teach self-catheterisation first.
From the UroRef Operative Quick Guide. Open the note page →
Every failure mode is its own module.
Timing and variation coverage are recorded for each module.
Urinary infection
Instrumentation, residual urine and catheterisation can contribute to symptomatic infection.
Applies to: All variantsRaised residual urine or retention
Reduced detrusor contractility may require temporary or ongoing catheterisation.
Applies to: All variantsHaematuria or bladder-wall injury
Needle puncture can cause bleeding and rarely deeper mural injury.
Applies to: All variantsInadequate or waning symptom response
Benefit may be partial or time-limited and should be distinguished from a technical complication.
Applies to: All variantsSystemic toxin effect
Rare distant neuromuscular symptoms require recognition and appropriate escalation.
Applies to: All variantsSources for this module
UK governance and shared-decision requirements for female continence surgery.
Accessed 2026-08-03 · opens source European Association of Urology EAU Guidelines on Non-neurogenic Female LUTSFemale continence, bulking, sling, colposuspension and related procedures.
Accessed 2026-08-03 · opens source European Association of Urology EAU Guidelines on Neuro-urologyBotulinum toxin, sphincterotomy, neuromodulation, augmentation and diversion.
Accessed 2026-08-03 · opens source British Association of Urological Surgeons Patient information leaflets by procedureUK patient-facing procedure, alternatives, recovery and complication framing.
Accessed 2026-08-03 · opens source