
Female mid-urethral sling surgery
Synthetic mid-urethral sling placement, separating retropubic and transobturator trajectories and their complication profiles.
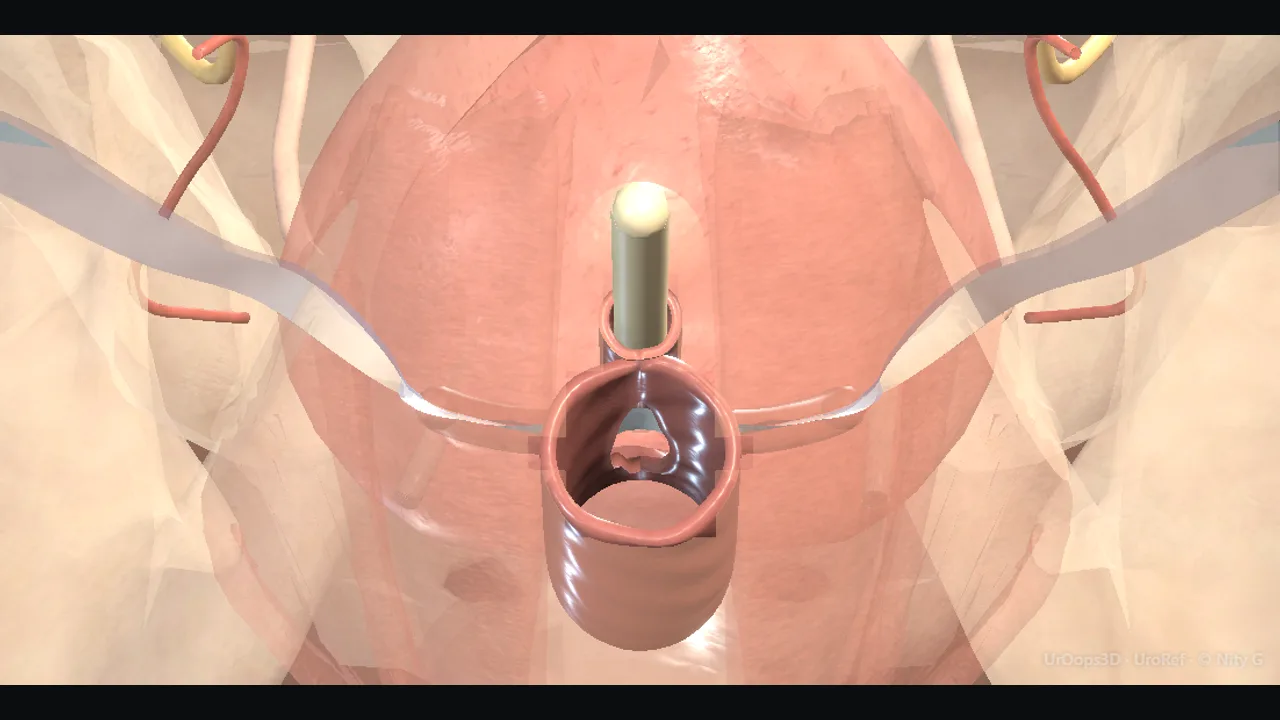 Interactive 3D Interactive operative model Open the 3D animation 3D Interactive retropubic sling
Teaching catalogue only. This coverage record is not a patient pathway or operative instruction.
Typical place in practice
Selected stress urinary incontinence after conservative options and mesh-specific informed consent in the applicable governance framework.
Alternatives and neighbouring procedures
Continence pessary, urethral bulking, autologous fascial sling, colposuspension or continued conservative management.
Same procedure family, explicit technique branches
These are variations of this canonical operation. Complication modules below identify whether they apply to all branches or only to named approaches.
Retropubic mid-urethral sling
Supports the mid urethra with arms exiting through the retropubic space.
Transobturator mid-urethral sling
Positions sling arms through the obturator route rather than the retropubic space.
Single-incision mini-sling
Uses a limited passage; device availability and evidence are system-specific.
High-level sequence
Coverage outline only; not a step-by-step technical guide.
- Confirm stress incontinence and emptying function
- Create a controlled para-urethral vaginal plane
- Pass the selected sling route with organ-protection checks
- Position without obstructive tension
- Close and confirm safe bladder emptying
Every failure mode is its own module.
Timing and variation coverage are recorded for each module.
Bladder, urethral or bowel injury
Trocar trajectory determines which organs are at risk; recognition during the procedure changes immediate management.
Applies to: All variantsBleeding or retropubic haematoma
Blind passage through the retropubic space can injure venous or arterial structures.
Applies to: Retropubic mid-urethral slingVoiding dysfunction or retention
Sling tension, swelling or pre-existing dysfunction can impair bladder emptying.
Applies to: All variantsMesh exposure or urinary-tract erosion
Synthetic material may become exposed in the vagina or erode into urethra or bladder.
Applies to: All variantsGroin, pelvic or sexual pain
Pain can follow vaginal dissection, mesh response or route-specific nerve and muscle injury.
Applies to: All variantsPersistent, recurrent or de novo urinary symptoms
Stress leakage may persist, while urgency or recurrent infection may newly appear or worsen.
Applies to: All variantsSources for this module
UK governance and shared-decision requirements for female continence surgery.
Accessed 2026-08-03 · opens source European Association of Urology EAU Guidelines on Non-neurogenic Female LUTSFemale continence, bulking, sling, colposuspension and related procedures.
Accessed 2026-08-03 · opens source British Association of Urological Surgeons Patient information leaflets by procedureUK patient-facing procedure, alternatives, recovery and complication framing.
Accessed 2026-08-03 · opens source