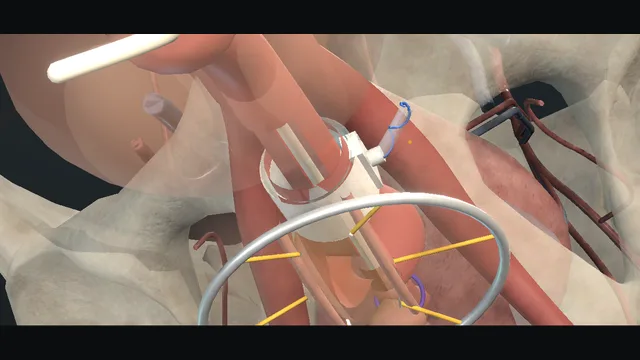
Schematic model of the Rigicon ContiClassic. Not device instructions for use.
Operative animation, AUS
Artificial urinary sphincter implantation
Built around the Rigicon ContiClassic® system: an occlusive cuff on the proximal bulbar urethra, a pressure regulating balloon in the prevesical space and a control pump in the scrotum.
The operation is won on the white tunica of the bulb, in sizing the urethra without compressing it, and in leaving the device deactivated while the urethra heals.
Advanced tierFRCS continence, functional urologyInteractive 3D
Operative visualisation
Open on a phone to use AR
Projector view, QR code, and your phone’s built-in AR viewer.
How to use this module. Play through the eleven steps, or use Back and Next. Open the Device panel to isolate a component, cycle the pump or read what can go wrong. Try a trigger to see a wrong move and its correction. Press Present for a full-screen run-through. Present this module
Lithotomy, the perineum from the foot of the table, and the other two spaces. Schematic, not to scale; relationships only.
One device, three spaces: in the perineum the cuff wraps the proximal bulbar urethra on its white tunica where the crura separate, the balloon sits in the prevesical space behind the lower abdominal wall, and the pump lies dependent in the scrotum, with the tubing tunnelled between them.
Erosion and atrophy are failures at the cuff-urethra interface.
›Bulbar urethra - the cuff site is the proximal bulbar urethra with robust spongiosum, approximately where the corpora cavernosa separate.
›Corpus spongiosum - invests the bulbar urethra; its white tunica is the plane, and entering the spongiosum bleeds and thins the cuff bed.
›Paired crura - diverge from the bulb toward the ischiopubic rami; where they separate marks the cuff site.
›Bulbospongiosus and perineal body - the muscle covers the bulb and is split in the midline; the perineal body lies behind the bulb.
›Prevesical space (space of Retzius) - reached here through a separate lower abdominal incision; the module places the balloon there.
›Pubic symphysis - the anterior landmark the urethra curves behind on its way from bladder neck to bulb.
›Scrotal pouch - the dependent pocket in front of the left testis for the pump; he has to be able to find it and squeeze it.
OrientationThe patient is in lithotomy and you are looking up at the perineum from the foot of the table. Scrotum and penis lie above, the anus below, and the bulb sits under the pubic arch between them. One device, three spaces: the cuff on the bulbar urethra, the balloon behind the lower abdominal wall and the pump in the scrotum. Before you start, name proximal and distal along the urethra.
Perineal exposureLift the scrotum forward and incise in the midline over the bulb with the blade. A ring retractor with hooks holds the skin edges; deepen through the fat until bulbospongiosus covers the field. Split the muscle along its midline raphe with the diathermy to reach the bulb beneath it.
The plane on the bulbDraw bulbospongiosus back and the corpus spongiosum lies beneath. This is the plane you are trying to develop: on the white tunica of the spongiosum, with the crura diverging either side. Before moving on, make sure you can identify the perineal body behind the bulb. A plane that starts to ooze has left the tunica. where it bites: a dissection outside the tunica opens the spongiosum, and the bleeding thins the bed the cuff must sit on.
Circumferential mobilisationA right-angle clamp passed in the dorsal plane, between spongiosum and corpora, frees the proximal bulbar urethra all round, on the tunica, where the crura separate. A loop follows it through once the plane is complete. Release only what the cuff needs. where it bites: a long bare segment may lose its blood supply, and it is the segment the cuff must heal onto.
SizingPass the sizer round the urethra without compressing it. That free reading chooses the cuff. The ContiRegular® cuff comes in twenty sizes from 3.5 to 13.0 cm, in 0.25 cm steps at the small end. A reading taken under squeeze is too small. where it bites: an undersized cuff is too tight on the urethra, and a tight cuff risks erosion.
Place the ContiRegular cuffWrap the ContiRegular® Occlusive Cuff round the proximal bulbar urethra, where the corpora cavernosa separate. How it closes follows the manufacturer's instructions, not this model. Its tubing leaves the cuff laterally, here on the left, toward the scrotum. The HydroShield™ coating is slippery when wet; the dipping solution is the surgeon's choice. where it bites: a cuff placed distally sits on thin spongiosum beyond the crura, away from the site the manufacturer names.
Pressure Regulating BalloonThrough a separate small transverse lower abdominal incision the muscle is held apart with retractor blades and a pocket is made in the prevesical space, the space of Retzius, behind the abdominal wall. The ContiClassic® Pressure Regulating Balloon is carried in collapsed on a forceps and filled there with sterile isotonic saline, as the instructions for use state; the fill volume is not stated in the instructions for use and is not taught here. It comes in five labelled ranges from 40-49 to 80-89 cmH2O. Which range suits a patient is the surgeon's decision and is not taught here. The fascia is closed round the tubing where it leaves. where it bites: a balloon in the wrong position can migrate, and the manufacturer names erosion of the balloon into the bladder.
Control PumpA long clamp from the abdominal wound opens a dependent pouch low in the scrotum, in front of the left testis. The ContiClassic® Control Pump follows it down the same tunnel and sits there with its deactivation button facing forward. He must be able to find it and squeeze it through the scrotal skin. A pump left high beside the cord may be hard to use. where it bites: a wrong pump position is one of the causes of migration the manufacturer names, and the pump can erode through the scrotum.
Tunnel and connectA clamp leads each line to the pump close to the pubis, one from the cuff and one from the balloon. Cut each to length, let the excess go, flush the ends and join them with EasyClick™ connectors, which need no assembly tool; the rubber-shod clamps come off last. No tension, no redundant loops. The tubing is reinforced against kinking, but a line cut to the wrong length can still kink. where it bites: wrong tubing length is a cause of migration the manufacturer names.
System checkSqueeze the pump: fluid leaves the cuff and passes to the balloon, and the cuff opens. Over the next two minutes the cuff gradually closes again. Then cycle the cuff open and press the deactivation button. Only with the cuff open and the device deactivated does any instrument pass the urethra: the catheter comes out and a flexible scope goes up to the cuff segment to confirm the mucosa is intact and there is no injury. The scope is withdrawn below the cuff before the button is released, and the lumen is watched coapting as the cuff refills. Check every connection before you close. where it bites: a scope or catheter passed through a closed cuff damages the urethra or the device; the cuff is deflated and the device deactivated first.
Deactivate and closeSqueeze once more to open the cuff, then press the deactivation button so it stays open. Hooks off; bulbospongiosus closed over the cuff with a running stitch, then the skin, then the abdominal wound, all with the device off. The instructions for use keep the device deactivated for four to six weeks after implantation, until scrotal swelling and pain have settled; activation follows in clinic by local protocol. Until then, and at any time after, no catheter or instrument passes the urethra until the cuff is deflated and the device deactivated.
The spatial relationships the animation is built to make automatic. Before you read each one, ask yourself: at this point in the operation, what is about to go wrong, and what is my first move? The save for each sits in the Complications tab.
RiskThe cuff-urethra interface - the device presses on a few centimetres of urethra; sizing without compressing it is what separates continence from erosion.
RiskThe mobilisation plane - off the white tunica the dissection opens the spongiosum; a scarred, thinned bulb is an erosion-prone bulb.
RiskThe irradiated pelvis - previous radiotherapy thins tissue and slows healing; erosion is reported more often and the counselling changes.
RiskThe scrotal pouch - a pump that is not dependent, or tubing under tension, may be hard to use; the manufacturer names pump erosion through the scrotum.
Trigger each of these live in the Animation tab, then read the save: the first move, the escalation trigger, and the line that goes in the op note.
Urethral erosion
tissue at the cuff-urethra interface breaks down and the cuff appears in the lumen; the manufacturer also names erosion of the pump through the scrotum and of the balloon into the bladder.
Previous radiotherapy is a recognised risk factor.
The save
Suspect it in any patient with a device who develops new perineal pain or swelling, haematuria, dysuria or a return of the leak.first move
Deactivate before any catheter: the safety information says the cuff is deflated and the device deactivated before any catheter or instrument passes the urethra.
Confirm with flexible urethroscopy, done by someone who knows the device is there; imaging is an adjunct.
Examine all three manufacturer sites: the cuff into the urethra, the pump through the scrotum and the balloon into the bladder.
Never force a catheter past a suspected erosion; if drainage is needed, a suprapubic route is considered.
An eroded cuff is removed, after senior review. Sepsis or a perineal collection needs urgent senior review.escalation trigger
Op note: cuff size and site, endoscopic findings, components removed, drainage plan and antibiotics.document
Device infection
wound or pocket infection in the early weeks, or later seeding; antibiotics alone rarely clear infection on an implant, and an infected device is usually removed in full.
The save
Recognise it early: redness, discharge or pain over any component, or fever with the device in.first move
Take cultures, start antibiotics, and assess the whole device, not only the obvious wound.
Plan removal in full: cuff, balloon, pump and tubing, after senior review.
An infected component left behind invites further infection and erosion.escalation trigger
Op note: cultures, components removed, debridement, antibiotic plan, and when re-implantation may be discussed.document
Recurrent incontinence: urethral atrophy
over time the urethra under the cuff may thin, so a device that cycles normally can stop holding.
The save
Take the history of the leak and of pump use: a device that cycles but no longer holds suggests atrophy.first move
Exclude erosion first: urethroscopy before any revision.
Check the device: fluid loss and pump position are other causes of a new leak.
Revision, such as a smaller cuff, is a senior decision made with the patient.escalation trigger
Op note: endoscopic findings, cuff size before and after, and the continence plan.document
When the case turns: the problem, then the next move.
ActionCircumferential dissection difficult - stay on the white tunica, pass a sling round the urethra and do not force a plane that is bleeding.
ActionCatheter needed in a patient with a device - deflate the cuff and deactivate the device first, as the safety information states; if in doubt, ask the implanting team.
ActionLeak persists after activation - work through cuff size and position, fluid loss and pump position before putting it down to the patient.
ActionPump hard for him to find or squeeze - check it sits dependent with the button forward, and re-teach him lying and standing; repositioning is a senior decision.
ActionLeak returns years later - assume atrophy or erosion until excluded: urethroscopy first, then a senior plan for revision.
The examiner stems this scene prepares you for. Try to answer out loud first, then reveal, and learn the discriminator, the detail that turns a pass into a strong pass.
QHow do you select patients for an artificial urinary sphincter after radical prostatectomy?reveal answer
The artificial urinary sphincter is the established surgical option for moderate to severe stress incontinence after radical prostatectomy once conservative treatment has failed.
I would confirm the leak is sphincteric, a demonstrable stress leak with a bladder that stores and empties, using urodynamics where the picture is mixed, treat any urge component first, and look at the urethra with flexible cystoscopy to exclude a stricture or bladder neck stenosis before implanting.
I would not rush: continence often improves through the first year, so I would document pad use with a pad test or diary once it has plateaued.
I would check that he has the dexterity and understanding to use a scrotal pump.
I would counsel on previous radiotherapy, which raises the risk of erosion and revision, on a period of deactivation after surgery, on the need to deactivate before any catheter, and on the realistic aim of social continence rather than complete dryness.
The male sling is discussed in the same conversation for milder leakage.
Strong pass
Stratify · gate · check
Stratify→By severity and radiotherapy
Gate→A sphincteric leak with a stricture-free urethra
Check→He can work the pump
Examiner note
Stratifying by severity and radiotherapy, naming a sphincteric leak with a stricture-free urethra as the gate before implantation, and checking that he can work the pump.
QA man presents three years after an AUS with perineal pain and new haematuria. What is the diagnosis and management?reveal answer
That is urethral erosion until proved otherwise.
I would ask about pump use and any recent catheter or instrumentation, and examine for perineal tenderness, swelling or induration.
The system represented here is the Rigicon ContiClassic, and its safety information names three erosion sites: the cuff into the urethra, the pump through the scrotum and the balloon into the bladder, so I would examine all three.
The safety information also says the cuff is deflated and the device deactivated before any catheter or instrument passes the urethra, so the device is deactivated first.
The diagnostic test is flexible urethroscopy, which may show the cuff in the lumen, with imaging if a collection is suspected.
I would never force a catheter past a suspected erosion; if he needs drainage, a suprapubic catheter is considered.
An eroded cuff comes out, and if infection has tracked along the tubing the whole device is removed.
That is a senior decision, made urgently if there is sepsis or a perineal collection.
Re-implantation is discussed later, once the urethra has healed.
Strong pass
Say all three
Naming urethroscopy as the diagnostic test
Deactivating before any catheter
Removing the cuff rather than observing it
Examiner note
Naming urethroscopy as the diagnostic test, deactivating before any catheter, and removing the cuff rather than observing it.
QWhen does device infection present and what is the principle of management?reveal answer
Infection presents in two patterns.
Early, in the first weeks after implantation, it is a wound or pocket infection: redness, discharge, pain over a component, and sometimes systemic sepsis.
Late infection is less common; it follows seeding from elsewhere or an erosion that has become infected, and it can appear years later.
The principle is that the device is a foreign body.
Once it is genuinely infected, antibiotics rarely clear it, and suppressing the picture only lets erosion of the urethra or the scrotal skin develop underneath.
I would take cultures and start antibiotics to control the acute episode, then plan removal of every component, cuff, balloon, pump and tubing, with debridement of the infected pockets.
After removal I would let the tissues heal, treat any urinary infection, and only discuss re-implantation after an interval.
That is why asepsis, minimal handling of the implant and antibiotic prophylaxis matter so much at the first operation.
Strong pass
Say both
Separating early wound infection from late seeding
Stating plainly that an infected device is removed in full: antibiotic salvage is not the plan
Examiner note
Separating early wound infection from late seeding, and stating plainly that an infected device is removed in full: antibiotic salvage is not the plan.
QWhy is the device left deactivated after implantation, and what does that mean for the patient?reveal answer
Because the urethra has just been mobilised all round and wrapped in a foreign body, and it needs to heal around the cuff before it tolerates repeated compression.
Activating straight away would press the cuff onto fresh, swollen and partly devascularised urethra, and ischaemia under the cuff is the mechanism of erosion.
So the device is deactivated at the end of the operation with the cuff open.
On the system represented here, the Rigicon ContiClassic, that is done with the deactivation button on the control pump.
The instructions for use keep the device deactivated for four to six weeks; activation follows in clinic by local protocol.
At activation I would confirm the cuff closes, teach him to find and squeeze the pump, and check that the cuff opens to let him void and closes again afterwards;
on this system the manufacturer describes the cuff closing gradually over about two minutes.
The practical rule lasts for life: the safety information says the cuff is deflated and the device deactivated before any catheter or instrument passes the urethra.
Strong pass
Say both
Linking the delay to the ischaemic mechanism of erosion
Adding the lifelong rule to deactivate before any catheter or instrument
Examiner note
Linking the delay to the ischaemic mechanism of erosion, and adding the lifelong rule to deactivate before any catheter or instrument.
Curriculum. Supports learning relevant to the ISCP Urology Curriculum syllabus topic Stress urinary incontinence in men and women. Not a workplace-based assessment and not evidence of competence.
Two minutes
Close the lap: recall it before you leave.
Say it aloud, then reveal. Reading is not remembering.
01The relationshipSay the critical spatial relationship out loud, then reveal.reveal
Memory frame
One device · three spaces
Cuff→Perineum
Balloon→Prevesical
Pump→Scrotum
Failure focus: cuff–urethra interface
Why?
One device, three spaces: in the perineum the cuff wraps the proximal bulbar urethra on its white tunica where the crura separate, the balloon sits in the prevesical space behind the lower abdominal wall, and the pump lies dependent in the scrotum, with the tubing tunnelled between them. Erosion and atrophy are failures at the cuff-urethra interface.
02The first moveUrethral erosion. Your first move?reveal
First move
Suspect erosion in any patient with a device
New perineal pain or swelling
Haematuria or dysuria
The leak comes back
Then: deactivate before any catheter passes.
More detail
Suspect it in any patient with a device who develops new perineal pain or swelling, haematuria, dysuria or a return of the leak.
03The escalation triggerUrethral erosion. What makes you call for help?reveal
Escalate when
Sepsis or a perineal collection: urgent senior review
An eroded cuff is removed, after senior review
Never force a catheter past a suspected erosion
Drainage needed: a suprapubic route is considered
More detail
An eroded cuff is removed, after senior review. Sepsis or a perineal collection needs urgent senior review.
04The discriminatorWhat turns a pass into a strong pass?reveal
Strong pass
Stratify · gate · check
Stratify→By severity and radiotherapy
Gate→A sphincteric leak with a stricture-free urethra
Check→He can work the pump
Examiner note
Stratifying by severity and radiotherapy, naming a sphincteric leak with a stricture-free urethra as the gate before implantation, and checking that he can work the pump.
05The pitfallWhere does this operation bite first?reveal
Pitfall
Size the urethra without compressing it
A reading taken under squeeze is too small: a tight cuff risks erosion.
Why?
The cuff-urethra interface: the device presses on a few centimetres of urethra; sizing without compressing it is what separates continence from erosion.
Revision practice with self-marked answers, not an assessment of clinical competence. Kept in
this browser only; it does not sync between devices.